What Is the Anion Gap?
The anion gap is a derived value that helps clinicians interpret electrolytes and assess acid-base balance. It is based on common blood test components, especially sodium, chloride, and bicarbonate. Because routine chemistry panels do not measure every charged particle in the blood, the anion gap estimates the difference between measured cations and measured anions, offering clues about unmeasured anions in the blood.
This makes the anion gap a helpful diagnostic tool in blood test interpretation, particularly when evaluating an electrolyte imbalance or an acid-base disorder. In practical terms, a change in the anion gap may point toward a hidden metabolic process that is not obvious from the test result alone. That is why it is often used as part of laboratory interpretation during a metabolic acidosis workup.
The value is typically reviewed alongside the rest of the serum electrolytes and broader blood chemistry. Although it is a calculated number, it can deliver meaningful clinical significance when interpreted correctly. A normal-looking panel may still hide a disorder if the anion gap is abnormal, which is why clinicians pay attention to the overall pattern rather than just a single test result.
How the Anion Gap Calculator Functions
An anion gap calculator uses a straightforward formula and your lab values to determine the anion gap fast. Rather than calculating it manually, you enter the measured concentration of sodium, chloride, and bicarbonate, and the medical calculator produces the result in seconds. This is useful for fast review of an electrolyte panel or basic metabolic panel.
The calculator is built to help users calculate anion gap without needing to remember the exact math each time. It is particularly useful when reviewing a serum bicarbonate value in context with the chloride level and overall normal electrolytes. The resulting anion gap value can support clinical thinking about whether the body is holding onto or losing acid, or whether there may https://anion-gap-estimator828.wpsuo.com/anion-gap-calculator-for-evaluating-lactate-elevation be excess unmeasured anions.
Because the calculator relies on routine lab measurements, it is a useful way to move from raw data to interpretation. Still, like any medical calculator, it should be viewed as a support tool rather than a replacement for clinical judgment. The same number can mean different things depending on the patient’s context, the reference range, and whether the value is corrected for albumin.
Anion Gap Formula and Calculation Steps
The common anion gap formula is written as:
Na - (Cl + HCO3)
In this formula, Na stands for sodium, Cl indicates chloride, and HCO3 indicates bicarbonate. This basic formula calculates the difference between measured positive and negative substances in the blood. The goal is to determine what is not directly measured, which can offer important clues about blood chemistry.
To work through it step by step:
- Locate the sodium value in the lab report. Identify the chloride value. Locate the bicarbonate or total CO2 value, depending on the report. Combine chloride and bicarbonate together. Take away that total from sodium.
For example, if Na is 140, Cl is 102, and HCO3 is 24, the calculation is 140 - (102 + 24) = 14. This value is the anion gap. That same approach is what the anion gap calculator performs automatically, helping users avoid arithmetic errors and speeding up laboratory interpretation.
In some clinical situations, a corrected anion gap may be considered if albumin is low. Since albumin is a major unmeasured anion, low levels can make the gap look deceptively low or normal. This is why a calculator that supports albumin adjustment can add value in a more complete metabolic acidosis workup.
What a Increased Anion Gap Means
A increased anion gap typically implies that more acids are found in the blood. This is often associated with acidosis, where the body either generates too much acid, fails to clear acid effectively, or releases bicarbonate in a way that shifts the balance. In this setting, the anion gap helps show whether the acidosis is related to unmeasured anions.
Two classic causes are lactic acidosis and ketoacidosis. Lactic acidosis may occur when tissues do not receive enough oxygen or when there is another process driving lactate buildup. Ketoacidosis can happen when the body breaks down fat rapidly and produces ketones that contribute to the acid load. In both cases, the elevated anion gap reading can be an key clue.
A high gap can also be seen with impaired kidney function, where the kidneys cannot remove acids efficiently. Other poisons may also raise the gap by introducing acids or acid-like substances into the system. Since many conditions can produce the same pattern, the anion gap should always be interpreted with the rest of the clinical picture and other lab findings.
In practice, a high gap is not a diagnosis by itself. It is a signal to look further. That may include checking the patient’s symptoms, reviewing the serum bicarbonate, and determining whether there is a broader acid-base issue. The diagnostic value lies in what the elevated value helps uncover.
What a Low Anion Gap Means
A low anion gap is less common, but it can still be meaningful. A common cause is low albumin, since albumin contributes greatly to the pool of unmeasured negative charges. When albumin drops, the calculated gap may fall even if the underlying chemistry is otherwise unchanged. In this case, an albumin-corrected anion gap may be more useful.
Another notable cause is multiple myeloma, a condition in which abnormal proteins can affect the balance of charges seen in blood chemistry. In some cases, these proteins may lower the measured gap or change how the numbers are interpreted. This is why the anion gap is not only about acid-base disorders; it can also point toward protein-linked changes in the bloodstream.
Lab error is also an key consideration. A low value can result from specimen issues, measurement variation, or problems with the reported lab values. Because of this, a surprising result should be reviewed carefully and, when needed, repeated. The anion gap is a valuable clue, but it should not be treated as definitive without context.
When a low result appears, checking the full electrolyte panel and reviewing serum electrolytes together can help determine whether the pattern reflects a genuine concern or simply an artifact. The result may also need to be viewed alongside the patient’s overall condition and any known electrolyte imbalance.
Typical Anion Gap Range and Reference Values
The expected range for the anion gap depends on the testing facility and the testing method used. This is why the best guide is the lab’s own reference limits and lab reference values. Various devices and reporting methods can shift the expected range, so a number that is normal in one setting may be borderline in another.
In general, the anion gap is interpreted in relation to the specific lab report, not as one universal number. The same principle applies when reviewing a metabolic panel or a broader electrolyte profile. Clinicians often pay attention to changes over time and the surrounding blood chemistry rather than a single isolated result.
If albumin is low, the apparent gap may diminish the true acid burden. In that situation, an albumin adjusted anion gap can better reflect the clinical picture. This is particularly important in patients with chronic illness, malnutrition, or inflammatory conditions where albumin may be reduced. Correcting for albumin helps support more accurate result interpretation.
Because the normal range varies, the best approach is to compare the measured result with the lab’s own range and interpret it in context. The calculator can quickly provide the number, but the normal range is what helps determine whether the value is low, normal, or high.
Typical Causes of Unexpected Anion Gap Findings
Unexpected values often suggest a variation in acid generation, acid clearance, or the distribution of measured and unmeasured ions. A leading cause of a high gap is kidney failure, because reduced kidney function limits the body’s ability to clear acids and maintain stable serum chemistry. This can contribute to metabolic acidosis and a rising gap.

Toxins are an additional major group. Certain toxic exposures can create a high gap by introducing acids or interfering with normal metabolism. Salicylates are a classic example and may produce complicated acid-base changes that affect the anion gap. In such cases, the calculator is only the first step; further testing and history are necessary.
Diarrhea often causes a different pattern. It can lead to bicarbonate loss and may be associated with a normal gap or non-gap metabolic acidosis, depending on the situation. Even when the gap is not high, the electrolyte pattern can still signal an acid-base problem. That is why the anion gap is best used as part of a wider diagnostic framework rather than in isolation.
Other abnormalities may arise from changes in albumin, unexpected laboratory results, or conditions such as multiple myeloma. In every case, the calculator helps structure the data, but the cause must be determined by the overall clinical picture and related testing.
Interpreting Outcomes With Related Blood Tests
The anion gap becomes more useful when assessed with other blood tests. One of the most important is the arterial blood gas, which offers direct information about pH, oxygenation, and acid-base status. If the pH is low and the anion gap is elevated, that supports the case for a high-gap metabolic acidosis. If the pH is normal, the situation may be more complex.
The bicarbonate level is also central to interpretation. A low bicarbonate often indicates the presence of acidosis, and the direction of change helps determine whether the issue is likely metabolic or related to compensation. The anion gap calculator uses bicarbonate directly, so the number is tightly linked to the broader acid-base pattern.
In some scenarios, the osmolar gap is also important. This can help identify certain toxic alcohol exposures or other causes of unexplained illness when the anion gap is elevated. Together, the anion gap and osmolar gap can support a more complete evaluation of suspected toxins or unexplained metabolic derangement.
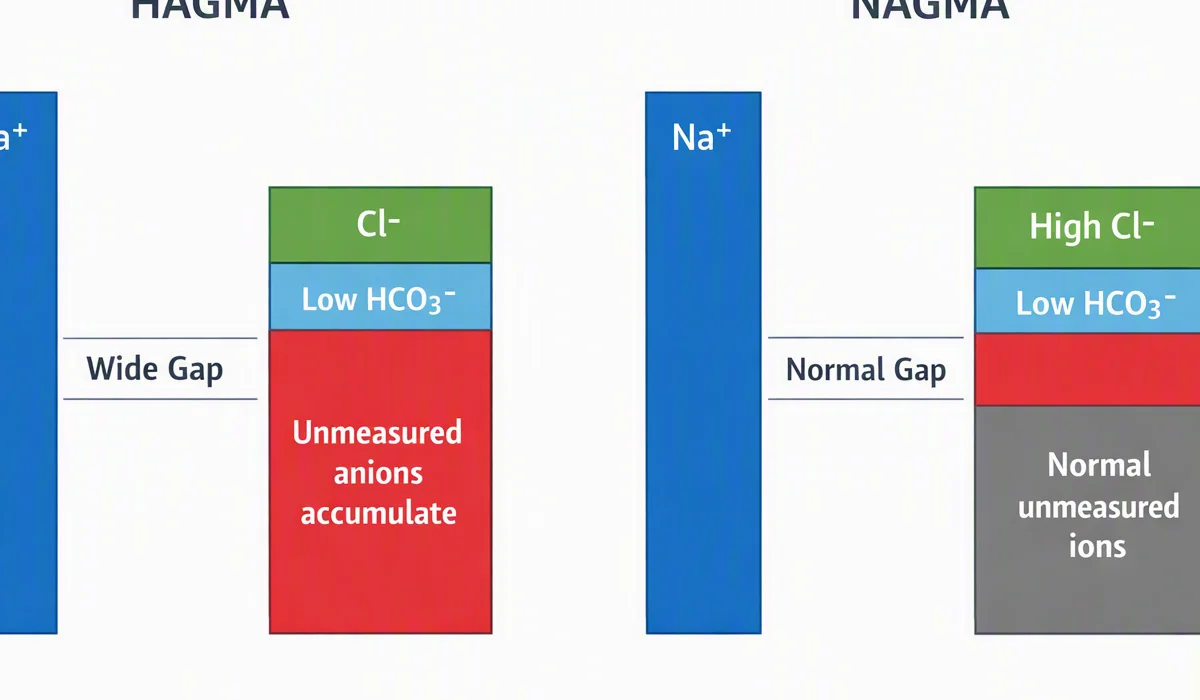
Putting these tests together helps create a clearer picture of the patient’s status. The anion gap is not a standalone answer; it is a piece of the full laboratory interpretation. When combined with blood gas data, bicarbonate trends, and other chemistry results, it becomes a practical part of an overall blood test interpretation.
Anion Gap Calculator FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to quickly estimate the anion gap from common lab values so you can interpret an electrolyte pattern more efficiently. It helps with blood test interpretation, especially when reviewing a basic metabolic panel or electrolyte panel. Clinically, it supports evaluation of acid-base balance and may help identify a hidden metabolic acidosis.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
The usual anion gap formula is Na - (Cl + HCO3). First, take the sodium value, add chloride and bicarbonate, and deduct that total from sodium. This is the same anion gap calculation used by a calculator, and it is commonly used in lab interpretation of serum electrolytes and blood chemistry.
What counts as a normal anion gap?
The normal range depends on the laboratory’s reference interval and reporting method. Because laboratory reference values vary, it is best to compare the result to the range printed on the report. If albumin is low, an albumin-corrected anion gap may provide a more accurate picture than the uncorrected result.
What might a high anion gap indicate?
A high anion gap often points to excess acid in the blood and is commonly associated with metabolic acidosis. Frequent causes include lactic acidosis, ketoacidosis, kidney failure, and certain toxins, including salicylates. It is a useful clue, but it should always be interpreted with the rest of the clinical picture.
Does albumin affect the anion gap result?
Yes. Albumin is one of the main unmeasured anions, so low albumin can lower the measured gap. That is why a corrected anion gap or albumin-corrected anion gap may be needed in some cases. If the result seems unexpected, it is also wise to consider lab error and review the full electrolyte panel before making conclusions.