What the Anion Gap Is and Its Importance
The anion gap is a valuable lab-derived value used to help identify the cause of metabolic acidosis and additional abnormalities in electrolytes. In the emergency department, it functions as a quick assessment tool for acid-base balance problems and assists clinicians refine a broad differential into a targeted diagnostic algorithm.
An anion gap calculator is valuable because the underlying concept is simple, but the interpretation is not. A patient may present with an apparently mild metabolic derangement, yet the pattern of serum electrolytes can reveal serious illness such as lactic acidosis, ketoacidosis, toxic ingestion, or renal failure. The gap represents the difference between measured cations and measured anions, which reflects unmeasured anions in the blood.
For emergency medicine, the anion gap is not just a number. It is a piece of clinical decision support that helps identify whether the patient likely has high anion gap metabolic acidosis, normal anion gap metabolic acidosis, or another acid-base disorder altogether. It also guides whether to obtain additional studies such as a venous blood gas, lactate, ketones, toxicology testing, or an osmolar gap.
How to Determine the Anion Gap
The typical anion gap formula is based on the main measured electrolytes: sodium, chloride, and bicarbonate. A common version is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Potassium is sometimes included in laboratories and references, but in urgent practice, the sodium-based formula is most common because it is straightforward, fast, and widely available on the basic metabolic panel. The result reflects the amount of anion deficit from unmeasured ions.
Example: if sodium is 140, chloride is 104, and bicarbonate is 20, the calculation is 140 − (104 + 20) = 16. That value may be normal or slightly high depending on the lab reference range and the patient’s clinical context.
An anion gap calculator streamlines this diagnostic calculation, limiting manual errors during time-sensitive critical care evaluation. It also helps clinicians rapidly review sequential results from an electrolyte panel when monitoring a patient’s response to treatment.
Using the Anion Gap Calculator in Emergency Medicine
In the ER, the calculator is especially useful when a patient has unexplained tachypnea, altered mental status, hypotension, vomiting, dehydration, or concern for anion gap clinical significance toxicity. It is typically used alongside the BMP, point-of-care testing, and occasionally blood gas analysis.
Rapid testing can provide rapid sodium, chloride, and bicarbonate values that allow clinicians to identify metabolic abnormalities early. This matters when the patient may be deteriorating and decisions about fluids, insulin, bicarbonate, antidotes, or dialysis need to be made without delay.
Practical use in the ER often follows this sequence:
- Examine the electrolyte panel and calculate the anion gap. Determine whether the patient has metabolic acidosis on a venous blood gas or arterial sample. Consider whether the pattern suggests elevated anion gap acidosis or non-gap metabolic acidosis. Pursue confirmatory tests such as lactate, beta-hydroxybutyrate, ketones, renal function, or toxicology studies.
The value of the calculator is not in serum anion gap formula isolation, but in the way it improves laboratory interpretation and supports early recognition of dangerous disease. In a busy ED workflow, it is one of the most efficient ways to screen for major acid-base pathology.
Typical, Increased, and Decreased Anion Gap Results
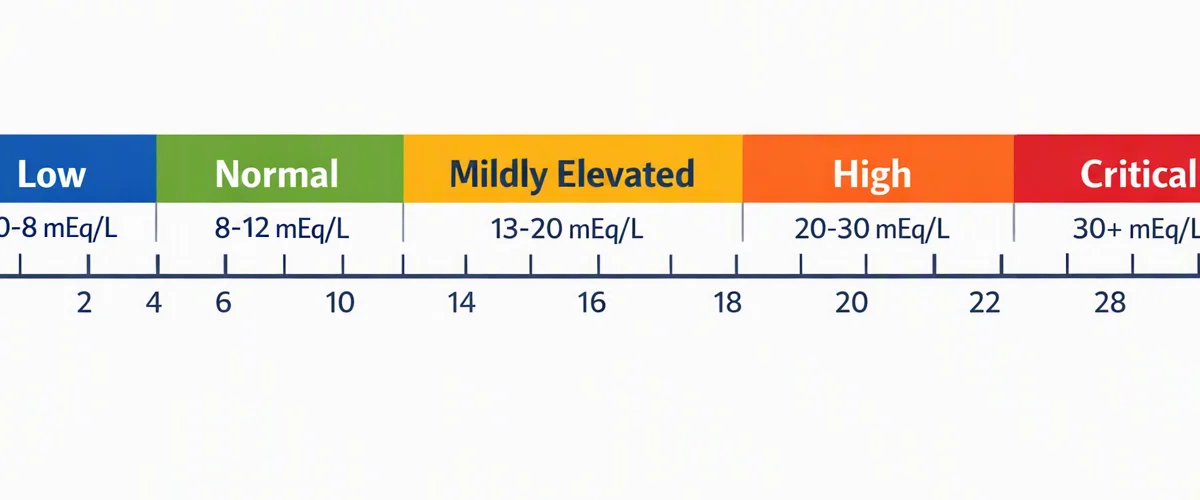
A normal anion gap usually suggests that any acidosis present is caused by loss of bicarbonate or chloride conservation rather than by build-up of unmeasured acids. However, “normal” depends on the laboratory method and comparison range, so clinicians should always read the value using local standards.
Increased anion gap metabolic acidosis points toward an excess of unmeasured acids in the blood. This is the result that often prompts urgent evaluation for lactic acid buildup, ketoacidosis, toxic alcohols, and renal failure. It is a key signal in metabolic assessment when a patient appears sick or has abnormal vital signs.
A low anion gap is less common and can be missed. It may occur with severe hypoalbuminemia, laboratory artifact, or occasionally other less common clinical conditions. Although a low value is not usually the main urgent issue, it should prompt review of the test result and the broader acid-base disorder.
For practical interpretation, the anion gap should be seen as a pattern based tool rather than a separate diagnosis. The presence of a normal or abnormal gap helps shape the next step in the diagnostic algorithm, not replace it.
Typical Causes of a Elevated Anion Gap
A number of conditions can result in high anion gap metabolic acidosis, and the emergency clinician should focus on rapid identification of critical causes. The most common and important include lactic acidosis, ketoacidosis, and use of toxic alcohols.
Lactic acidosis often develops in shock, hypoperfusion, seizures, severe infection, or tissue ischemia. In the ED, this is a major concern in patients with possible sepsis, hypotension, or respiratory compromise. The anion gap may climb as lactate accumulates and depletes bicarbonate during buffering.
Ketoacidosis occurs when ketone bodies build up as organic acids. Diabetic ketoacidosis is the common emergency presentation, but starvation or alcoholic ketosis can also play a role. The bicarbonate level often drops significantly, and the anion gap rises because ketones are unmeasured anions.
Toxic alcohols are another important cause of a high gap. Ethylene glycol and methanol are especially important because they can cause serious organ injury and may initially present with nonspecific symptoms. In these cases, the anion gap may rise later in the course, so timing matters. An elevated gap with suspicion of ingestion should prompt consideration of an osmolar gap and immediate toxicity screening.
Additional causes may exist, but these three are the main emergency priorities because they are urgent and potentially reversible with prompt treatment.
Frequent Causes of Normal Anion Gap Acidosis
Normal anion gap acidosis is frequently related to loss of bicarbonate or limited acid excretion. The hallmark lab pattern often includes a drop in bicarbonate with a secondary chloride elevation, creating hyperchloremia-related acidosis.
Diarrhea is a frequent cause. Gastrointestinal bicarbonate loss can lower serum bicarbonate while chloride rises to maintain electrical neutrality. This is a classic example of how the chloride shift helps keep the numbers balanced while the patient remains metabolically acidotic.
RTA is another important cause. In this setting, the kidneys cannot adequately acidify the urine or retain bicarbonate, leading to continued acidosis despite a normal anion gap. It is important to recognize this because it may suggest an underlying or chronic kidney issue rather than a transient illness.
Normal anion gap acidosis can also occur after large-volume saline administration, though the main urgent causes to keep in mind remain gastrointestinal losses, RTA, and kidney bicarbonate loss. Careful review of fluids, medications, and recent illness helps tell these patterns apart.
How Exactly Does the protein albumin Alter the anion gap
the protein albumin is the primary hidden anion in plasma, so a reduced albumin level can falsely lower the anion gap. This is important because a patient may have a important acidosis that appears less severe on the initial calculation.
That is why clinicians often use a corrected anion gap when decreased albumin is present. A common approach is to adjust the measured gap upward when albumin is below normal, allowing detection of hidden excess acids. The precise correction formula can vary by facility, but the principle is the same: low albumin can hide a dangerous elevation.
This adjustment is especially relevant in critical care and in patients with hepatic disease, malnutrition, inflammation, or chronic illness, where low albumin is often seen. Without correction, the anion gap may underestimate the true degree of metabolic derangement.
In practice, a corrected calculation improves laboratory interpretation and can reveal a masked high gap when the raw result appears falsely normal. That is one reason the anion gap calculator is most useful when combined with albumin data rather than used alone.
Sequential Interpretation in the ED
Evaluating the anion gap in the emergency department should take a clear approach. The goal is to recognize the underlying acid-base disorder promptly and see whether immediate treatment is needed.
Step 1 — Verify the chemistry values. Review sodium, chloride, and bicarbonate from the basic metabolic panel or point-of-care source. Make sure the result is plausible and not obviously affected by laboratory error.
Step 2: Assess whether the patient has metabolic acidosis on a venous blood gas or other blood gas measurement. A low bicarbonate alone is not enough; pH and respiratory compensation help outline the full picture.
Then: Sort the gap as normal, elevated, or low. If elevated, think first about lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. If normal, look for bicarbonate loss or chloride excess.
After that: If the presentation suggests ingestion, check the osmolar gap. An elevated osmolar gap with metabolic acidosis increases concern for toxic alcohol exposure, especially when clinical findings are unclear.
Step 5 — Weave together all findings with the story. The same lab result means something different in a stable patient with mild diarrhea than in a hypotensive patient with altered mentation and respiratory distress.
This organized method is essentially a bedside diagnostic algorithm that integrates the calculator with patient status, blood gas data, and additional labs. It is a practical example of metabolic evaluation in real-time care.
Drawbacks and Caveats of the Calculator
Like any diagnostic calculation, the anion gap calculator has limitations. Small differences in lab methods can create measurement variation, so the exact normal range can differ between institutions and analyzers.
Laboratory error can also mislead interpretation. Hemolysis, specimen handling issues, or inconsistent repeat values may produce a result that does not fit the clinical picture. When the number and the patient do not match, repeat testing and correlation with other data are essential.
The calculator does not replace clinical context. A small increase may still be very important in a poisoned, unstable patient, while a more dramatic number may be long-standing or partly compensated in a patient with known kidney disease. The anion gap should thus be viewed as part of the full clinical context rather than as a standalone prompt.
Other pitfalls include ignoring albumin, assuming every high gap is due to one cause, or failing to look for a mixed disorder. The best interpretation usually comes from combining the anion gap with blood gas findings, kidney function, ketones, lactate, and toxin screening when indicated.
When to Escalate Evaluation or Treatment
Escalate without delay when the anion gap suggests a serious condition such as sepsis, renal failure, or poisoning. These are more than laboratory abnormalities; they are critical emergencies that can worsen quickly without treatment.
In suspected sepsis, an elevated gap plus elevated lactate or hemodynamic instability should trigger rapid resuscitation, cultures, antimicrobial therapy, and source evaluation. In renal failure, worsening acidosis may require nephrology input, close electrolyte monitoring, and possible renal replacement therapy depending on the overall picture.
For suspected poisoning, especially with toxic alcohols, ethylene glycol, or methanol, do not hold off for confirmatory results if the clinical suspicion is high. The combination of acidosis, elevated gap, and possible osmolar gap can justify urgent antidotal therapy and consultation with toxicology.
It is also appropriate to escalate when the patient has worsening mental status, respiratory fatigue, shock, or rapidly changing laboratory values. The calculator should direct the next step, not hold it up.
Frequently Asked Questions
What is the anion gap calculator used for?
The anion gap calculator is used to swiftly estimate the anion gap from serum sodium, chloride, and bicarbonate values. In emergency medicine, it helps clinicians identify metabolic acidosis, classify acid-base disorders, and decide whether further evaluation for lactic acidosis, ketoacidosis, toxic alcohols, or renal failure is needed.
What is the normal range for the anion gap?
The normal range depends on the testing method and reference value used by that laboratory. Because testing techniques vary, clinicians should interpret the value using the facility’s range rather than relying on a single universal cutoff. In practice, the result is best understood in together with the patient’s symptoms, bicarbonate level, and overall acid-base balance.
How do you calculate a corrected anion gap for albumin?
To estimate a corrected anion gap, clinicians adjust the measured result upward when albumin is low because hypoalbuminemia can hide a true elevation. The exact correction method can vary, but the goal is the same: account for the effect of low albumin on the gap so that significant metabolic acidosis is not missed. This is especially useful in patients with chronic illness, liver disease, or critical illness.
What causes a high anion gap in emergency medicine?
The most important causes of high anion gap metabolic acidosis in emergency medicine include lactic acidosis, ketoacidosis, and toxic alcohols such as ethylene glycol and methanol. Other important causes include sepsis and renal failure. The anion gap should be interpreted with blood gas results, lactate, ketones, renal studies, and the patient’s overall presentation.
When is it appropriate to an osmolar gap be checked with anion gap results?
An osmolar gap should be checked when there is concern for ingestion, especially if the patient has unexplained acidosis, altered mental status, or a history that suggests possible exposure to toxic alcohols. It is particularly useful when evaluating possible ethylene glycol or methanol poisoning. In the ED, the osmolar gap adds another layer of toxicology screening to the broader metabolic evaluation.