What the Anion Gap Shows in Blood Chemistry
The anion gap is a derived value used in medical chemistry to aid in interpreting electrolytes and assess acid-base balance. It reflects the difference between major measured cations and anions in the blood, mainly sodium and chloride, with bicarbonate included in the comparison. Because routine testing does not directly measure every ion in circulation, the anion gap helps reveal the presence of unmeasured anions and other shifts in the body’s buffering system.
In practical lab interpretation, the anion gap is a diagnostic aid rather than a definitive diagnosis. It is often used to assess a possible acid-base disorder, especially when a clinician is trying to determine whether a metabolic disturbance is present. A normal result suggests the measured ions are balanced in a way that fits the expected electroneutrality of plasma, while an abnormal result can point to an electrolyte imbalance or hidden acids that are not obvious from the basic panel alone.
How an Anion Gap Calculator Functions
An Anion Gap Calculator applies a basic formula to the values input from a lab report. Typical calculators use serum sodium, serum chloride, and serum bicarbonate, and some also include potassium. The calculator then gives a computed value that assists lab interpretation by revealing whether the measured ions suggest an acid-base issue.
In the usual approach, the calculator subtracts chloride and bicarbonate from sodium. If potassium is included, the formula may adjust slightly, but the basic idea is the same: contrast major measured ions against the expected balance. Because the result is a calculated value, its meaning depends on the surrounding serum electrolytes, the patient’s clinical state, and the interpretive context of the rest of the report.
This makes the calculator useful as a diagnostic marker in clinical chemistry. It does not substitute for direct testing or clinical judgment, but it helps determine whether the lab result may reflect an anion deficit, anion excess, or a broader metabolic disturbance.
Conventional Anion Gap Formula and Reference Range
The traditional anion gap formula is usually written as:
Anion gap = sodium − (chloride + bicarbonate)
A few laboratories also use a potassium-inclusive variation, but the sodium-based version is the most commonly used in routine lab science. The result is then compared with a normal range or reference interval provided by the laboratory performing the test.
The exact reference interval can vary because different instruments, reagents, and reporting methods may produce slightly different values. That is why the result should always be interpreted against the lab’s own serum chemistry panel reference interval rather than relying on a universal cutoff. A result that appears abnormal in one lab may fall within another lab’s normal range.
From a lab science perspective, the anion gap is a useful summary of the relationship between measured ions and unmeasured ions. It is not a direct measurement of acid or base, but rather a calculated clue that may indicate the need for further testing, including a blood gas or additional chemistry studies.
Revised Anion Gap for Albumin
Albumin is a major unmeasured anion in blood, so low albumin can decrease the apparent anion gap. This is why many clinicians and laboratorians use a corrected anion gap when the patient has hypoalbuminemia. Without albumin correction, the result may diminish the presence of an acid load.
The corrected value is especially important in patients with illness, inflammation, malnutrition, liver disease, or fluid shifts that reduce albumin concentration. In these cases, the unadjusted anion gap may look normal even though a true acid-base problem exists. An albumin-adjusted interpretation helps reveal the hidden contribution of the reduced protein buffer.
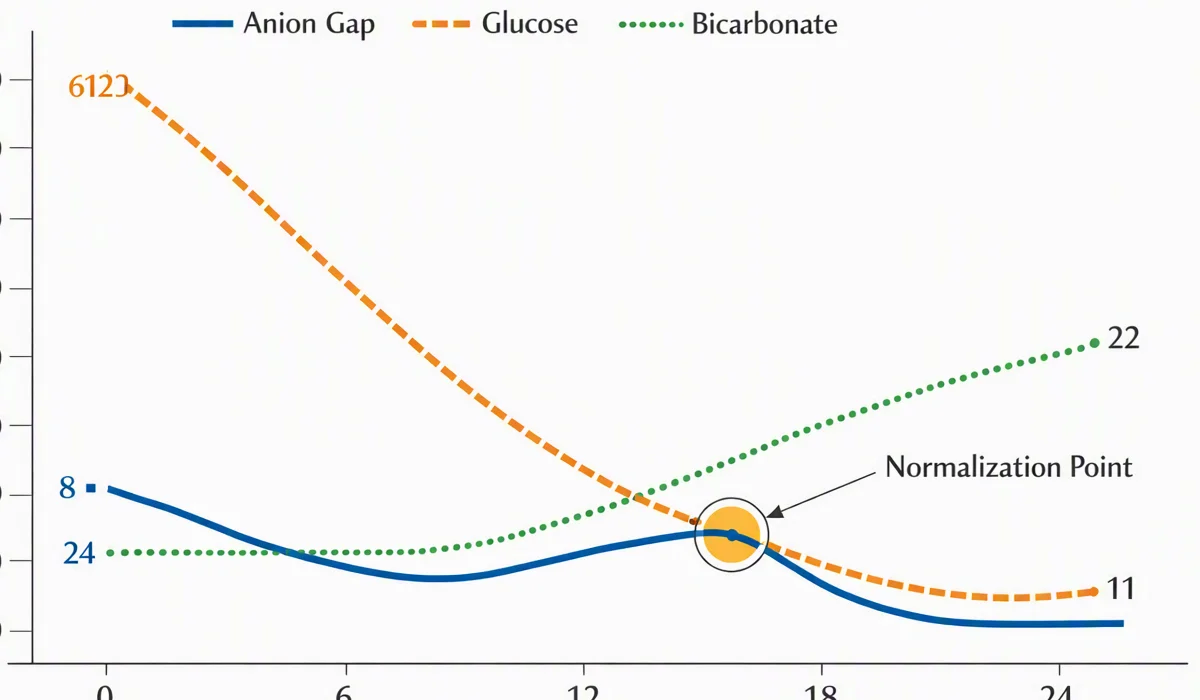
For lab interpretation, albumin correction improves the utility of the anion gap as a diagnostic aid. It reinforces the connection between the numeric result and the patient’s real metabolic state. In other words, the corrected anion gap provides better interpretive context when low albumin could otherwise mask clinically important changes.
Raised Anion Gap compared with Low Anion Gap
A elevated anion gap usually points to too much acid or buildup of unmeasured anions. This pattern is often linked to metabolic acidosis, where bicarbonate is depleted as the body buffers acid. A high value is a indication that the balance between measured ions and unseen ions has shifted in a meaningful way.
A decreased anion gap is less common and can be due to lab or physiologic factors. It may reflect low albumin, abnormal proteins, or analytical issues, among other possibilities. Because the low result can be subtle, it is important to check the numbers and review the broader electrolyte panel before drawing conclusions.
Both patterns require close lab interpretation. A high result often indicates added acids, while a low result may suggest reduced negative charge from albumin or testing-related issues. Either way, the value should be read as part of the full clinical picture rather than as an isolated finding.
Frequent Causes of an Abnormal Anion Gap
Various factors can shift the anion gap away from the expected interval. One of the most important is lactic acidosis, in which lactate accumulates as tissues generate energy under stress or inadequate oxygen supply. Another common cause is ketoacidosis, where ketone production goes up and contributes additional acids to the blood.
Renal failure can also result in an abnormal result because the kidneys are less able to clear acid and support normal electrolyte handling. As retained acids and related compounds build up, the gap may increase. In addition, toxins can trigger a high anion gap by adding unusual acids or by interfering with metabolism in ways that increase acid load.
These factors fit the same basic pattern: the body accumulates unmeasured ions or loses buffering capacity, and the calculated value rises. In the lab, this makes the anion gap a useful clue in distinguishing one metabolic disturbance from another.
How to Operate the Calculator Step by Step
Using an Anion Gap Calculator is simple when the lab values are available. First identify the input values from the report, then enter the serum sodium, serum chloride, and serum bicarbonate. When available, include potassium as well.
Once you enter the numbers, review the calculated result and compare it with the lab’s reference range. If the calculator offers a corrected output, enter the albumin value so the tool can estimate the corrected anion gap. This matters especially when hypoalbuminemia is present.
After the calculation is finished, interpret the result in context. A single number cannot diagnose an acid-base disorder by itself. Instead, use it as part of a wider assessment that includes the electrolyte panel, the serum chemistry panel, and any other available clinical information.
Patient and Laboratory Interpretation Tips
Effective clinical interpretation opens with verifying whether the result fits the overall picture of acid base balance. Should the anion gap is increased, watch for signs of metabolic acidosis and consider whether the patient may have lactic acidosis, ketoacidosis, renal failure, or toxin exposure. When the value is reduced, check albumin, total protein, and the possibility of analytical variation.
A blood gas can be very helpful because it offers direct information about pH, carbon dioxide, and bicarbonate handling. When paired with the anion gap, it gives a stronger view of whether there is a true acid-base disorder and whether compensation is occurring. This combination is often more revealing than any one lab result alone.
It is also important to consider analytical pitfalls. Small shifts in measured ions can change the calculated value, and differences between instruments can affect the reported reference interval. For this reason, the anion gap should be interpreted alongside the electrolyte panel, the serum chemistry panel, and the patient’s clinical status. That approach enhances diagnostic clarity and reduces the risk of overcalling or missing an abnormality.
Anion Gap Calculator FAQs
What is an anion gap calculator used for?
An Anion Gap Calculator is used to estimate the anion gap from lab values and anion gap lab interpretation help assess electrolyte balance, acid-base balance, and possible metabolic acidosis. It is a clinical aid that supports lab interpretation by highlighting changes in measured ions and unmeasured ions.
What is the normal anion gap range?
The normal range depends on the laboratory and its reference interval. Different methods and instruments can produce different expected values, so the result should always be compared with the range reported on the specific serum chemistry panel.
Why does low albumin affect the anion gap?
Albumin is a major unmeasured anion, so hypoalbuminemia can lower the measured anion gap. That is why an albumin correction or corrected anion gap is often needed to avoid missing an underlying anion gap clinical significance acid-base disorder.
What can cause a high anion gap?
A high anion gap is often linked to lactic acidosis, ketoacidosis, renal failure, and certain toxins. These conditions increase unmeasured anions or impair the body’s ability to maintain acid-base balance.
Should an anion gap be assessed with other lab results?
Yes, it should. The anion gap should consistently be interpreted with the electrolyte panel, blood gas, albumin, and the rest of the clinical picture. That combined approach improves clinical interpretation and helps distinguish a true metabolic acidosis from other lab patterns.