What’s the anion gap?
The AG is a practical method to review electrolytes and explain the balance between measured and unmeasured anions in the blood. It is usually calculated from a serum chemistry panel and helps clinicians focus the differential diagnosis for acid-base issues, especially metabolic acidosis.
From a physiology standpoint, the anion gap shows the disparity between the main measured cations and anions in serum. Because routine testing does not directly measure every ion, the calculated value suggests the amount of unmeasured ions available. This makes the anion gap a practical tool for clinical interpretation and laboratory assessment when evaluating an acid-base disturbance.
Medical students often initially encounter the anion gap as part of a broader serum chemistry or electrolyte panel. It is especially important because a change in the gap can reveal a hidden metabolic derangement even when the pH has not yet been reviewed. In other words, the anion gap is not just a number; it is a signal to the underlying acid-base balance.
How to Determine the Anion Gap
The anion gap formula is often expressed as:
Anion gap = sodium − (chloride + bicarbonate)In this calculation, sodium is the main measured cation, while chloride and bicarbonate are the measured anions. An anion gap calculator automatically performs this math from the lab values you enter, helping lower arithmetic errors during a busy clinical workflow.
The calculator is easy to use:
- Enter the serum sodium value. Enter the serum chloride value. Type in the serum bicarbonate value. The calculator returns the anion gap and often shows whether it is elevated or within the expected reference interval.
For example, if sodium is 140, chloride is 104, and bicarbonate is 24, the anion gap is 12. In many laboratories, this is regarded as normal. The exact interpretation depends on the lab’s reporting method and local reference range, so students should always compare the result with the values provided by the institution.
Knowing the formula is important because the result is only as reliable as the underlying data. If any value is inaccurate due to a measurement error, the calculated anion gap may be misleading. That is why clinicians should always interpret the output in the context of the broader electrolyte disorder and the patient’s clinical picture.
Normal Range and Albumin Correction
A normal anion gap is commonly set by the laboratory’s reference range, which may vary depending on the analyzer and whether potassium is included in the equation. A common without potassium reference interval is roughly 8 to 12 mEq/L, but this should not replace the local lab standard.
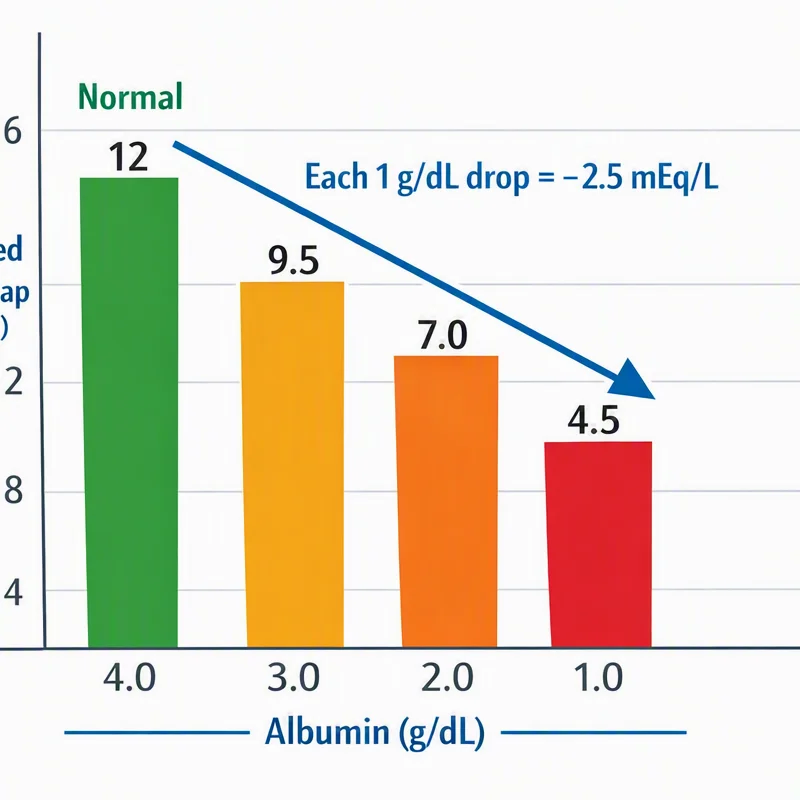
One of the most essential adjustments in real practice is the effect of albumin. Because albumin is a major unmeasured anion, reduced albumin can make the anion gap appear artificially low or normal even when an acid load is present. This is why albumin correction is often essential for accurate interpretation.
A practical way to think about it: when albumin falls, the measured anion gap falls too, because fewer negatively charged proteins are contributing to the total. A corrected result helps identify an elevated gap that might otherwise be missed. In many teaching settings, a commonly used correction is to add approximately 2.5 mEq/L to the anion gap for every 1 g/dL decrease in albumin below 4 g/dL. However, students should follow local teaching standards and institutional methods.
This is especially important in hospitalized patients, where hypoalbuminemia is common. Without albumin correction, clinicians may miss the severity of metabolic acidosis. A normal-looking result on an anion gap calculator does not always mean the acid-base picture is normal.
Medical Analysis of an High Anion Gap
An increased anion gap indicates the occurrence of additional acids or other unmeasured ions in the serum. This finding is typically seen in high anion gap metabolic acidosis, a central topic in acid-base medicine. In this context, the body accumulates acids, and bicarbonate is used up as buffering occurs.

Common causes include lactic acidosis, ketoacidosis, and uremia. Each has a different pathophysiology, but all can produce a raised gap:
- Lactic acidosis: elevated lactate from tissue hypoperfusion, sepsis, severe exercise, or impaired lactate clearance. Ketoacidosis: build-up of ketone bodies in diabetic, alcoholic, or starvation states. Uremia: retention of acids in advanced kidney failure, adding to the burden of unmeasured anions.
When the gap is elevated, the next step is not merely to label the disorder. Students should ask why the acid is occurring, how advanced the derangement is, and whether there are other abnormalities. The anion gap helps with diagnostic approach, but it is only one piece of the puzzle.
For example, a patient with vomiting, altered mental status, and elevated glucose may have ketoacidosis. Another patient with hypotension and rising lactate may have lactic acidosis. A third patient with renal failure and elevated creatinine may have uremia. In each case, the same calculator output requires distinct clinical interpretation.
Reasons for a Typical Anion Gap Metabolic Acidosis
Not every metabolic acidosis causes an elevated gap. Normal anion gap metabolic acidosis, also called non-anion gap metabolic acidosis, occurs when bicarbonate is removed or chloride increases to maintain electroneutrality. In this pattern, the anion gap remains in the normal range even though the patient is acidotic.
The chief causes are diarrhea and renal tubular acidosis. With diarrhea, the gastrointestinal tract loses bicarbonate, producing loss of bicarbonate and a fall in serum bicarbonate. With renal tubular acidosis, the kidneys fail to reabsorb bicarbonate appropriately or fail to excrete acid, leading to a persistent acid-base problem despite maintained or only mildly impaired kidney function.
In practice, the body often responds by elevating chloride, which is why hyperchloremic acidosis is another typical way to describe this pattern. Students should note that the absence of an elevated anion gap does not mean there is no important acid-base disturbance. It simply points toward a different mechanism.
A step-by-step evaluation should include the history, medication use, kidney function, gastrointestinal losses, and the broader electrolyte pattern. This kind of diagnostic approach is better than relying on a calculator result alone.
Systematic Approach to Acid-Base Disturbances
To assess any acid-base imbalance, medical students should work in a stepwise order rather than going straight to one number. The process starts with the ABG, then moves to serum electrolytes, then to the anion gap, and finally to compensation and mixed disorders.
A useful stepwise method is:
- Check the arterial blood gas for pH, CO2, and bicarbonate. Figure out whether the primary problem is metabolic or respiratory. Apply the anion gap to divide metabolic acidosis as high gap or normal gap. Review the compensatory response to see whether respiratory response is appropriate. Consider the delta ratio if the anion gap is elevated to look for additional disorders.
The delta gap helps show whether the rise in the anion gap is proportional to the fall in bicarbonate. If the change does not align with expectations, a mixed acid-base disorder may be present. This matters because a patient can have more than one process at the same time, such as high anion gap metabolic acidosis plus metabolic alkalosis from vomiting.
Compensation should always be assessed because the body responds predictably to primary metabolic disturbances. For example, in metabolic acidosis, the respiratory system usually lowers CO2 through hyperventilation. If compensation is absent or excessive, another process may also be occurring.
This framework turns the anion gap calculator into more than a formula tool. It becomes part of a broader systematic evaluation of the patient’s acid-base status.
Common Pitfalls When Using an Anion Gap Calculator
A frequent pitfall is failing to account for albumin. Because hypoalbuminemia reduces the apparent gap, students may fail to identify a clinically important high-gap state unless they apply the corrected anion gap. This is particularly important in critically ill patients, where low albumin is common.
One other mistake is relying on the calculator without checking the actual lab values. The anion gap is only useful if sodium, chloride, and bicarbonate are correct and comparable. A single transcription error can change the result enough to affect the interpretation.
Students also sometimes forget that a “normal” value does not rule out disease. A patient with severe hypoalbuminemia may have a deceptively normal result even in the presence of significant acid generation. Likewise, a mixed acid-base disorder can hide behind a seemingly straightforward number.
More mistakes include:
- Not checking the laboratory’s reference interval. Overlooking the role of measurement error in electrolyte testing. Failing to connect the result with the patient’s symptoms and diagnosis. Believing all metabolic acidosis is high gap.
The best habit is to view the calculator as an assistant, not a replacement for thinking. Accurate interpretation requires considering the result with the clinical story, blood gas analysis, and the broader metabolic context.
Study Cases for Future Clinicians
Clinical case 1: A patient presents with a serum sodium of 138, serum chloride of 100, and serum bicarbonate of 14. The anion gap is 24, indicating elevation. This pattern clearly suggests high-gap metabolic acidosis. The next step is to think about causes including lactate-related acidosis, ketoacidosis, and uremia, then correlate with vitals, glucose, creatinine, and lactate.
Example 2: A patient comes in after multiple days of intense bowel losses. Serum sodium is 140, serum chloride https://anion-gap-chart421.talesignal.com/posts/can-paraproteinemia-reduce-the-anion-gap is 112, and serum bicarbonate is 18. The anion gap is 10, which is within the usual range. This fits with normal anion gap metabolic acidosis caused by loss of bicarbonate. The higher chloride level supports a hyperchloremic pattern.
Clinical case 3: The patient has advanced kidney disease with sodium 135, chloride 98, and bicarbonate 15. The anion gap is 22, pointing to retained acids and possible renal uremic acid retention. If the albumin level is low, the albumin-adjusted calculation may reveal an even higher corrected value. That corrected number offers improved clinical reading than the raw number alone.
Case 4: A person with type 1 diabetes shows sodium 130, chloride 95, bicarbonate 8, and signs of dehydration. This pattern indicates ketoacidosis. In this setting, the anion gap calculator helps confirm the presence of a high-gap metabolic process, but treatment decisions depend on the full clinical picture, including glucose, ketones, potassium, and blood gas analysis.
These examples show why the calculator is a starting point. What matters most is connecting the number with pathophysiology, diagnosis, and management.
FAQs
Why use an anion gap calculator?
An Anion Gap Calculator is designed to calculate the difference between measured cations and anions from routine labs. It helps evaluate acid-base acidosis, identify unmeasured acids, and guide the workup strategy to acid-base problems. It is especially useful in recognizing high-gap metabolic acidosis and deciding whether albumin correction is needed.
How do you determine the anion gap using lab values?
Apply the anion gap formula: sodium minus the sum of chloride and bicarbonate. In formula form, it is sodium − (chloride + bicarbonate). Input the values into an anion gap calculator to minimize arithmetic mistakes, then match the result with the local reference range.
What is a normal anion gap range?
The normal range is based on the laboratory method and whether potassium is included. Several laboratories use a non-potassium range around 8 to 12 mEq/L, but students should always use the institution’s stated reference interval. A “normal” value must also be interpreted in light of albumin and the broader clinical picture.

Why do you correct the anion gap for albumin?
You adjust for albumin because it is a major unmeasured anion. In hypoalbuminemia, the measured gap may seem falsely low or normal, which can hide a true acid-base problem. Albumin correction produces a more accurate corrected value and improves clinical interpretation.
What leads to a high anion gap metabolic acidosis?
Major causes include lactic acidosis, ketoacidosis, and uremia. These conditions raise unmeasured ions and lower bicarbonate, producing high anion gap metabolic acidosis. A careful review of the arterial blood gas, electrolytes, kidney function, glucose, and lactate helps confirm the cause.