What the Anion Gap Reflects
The anion gap is a derived value from a routine electrolyte panel that supports the assessment of blood test interpretation in suspected acid-base problems. It represents the relationship between major measured ions, especially serum sodium, serum chloride, and serum bicarbonate. In simple terms, the anion gap approximates the amount of unmeasured ions in the blood and can serve as a practical diagnostic marker for certain metabolic problems.
Because the body works to maintain electroneutrality, the sum of positive and negative charges in blood should stay balanced. When measured ions shift, the anion difference can indicate an underlying acid-base disorder. A change in the gap often indicates a metabolic derangement such as metabolic acidosis, where acids accumulate or bicarbonate is reduced.
The concept is especially useful in serum chemistry because it gives clinicians a rapid clue about whether the patient may have a high anion gap, a normal anion gap, or a low anion gap. That clue can narrow the list of possible causes and direct further testing.
How an Anion Gap Calculator Works
An anion gap calculator relies on a basic calculation formula built on common laboratory values. Usually calculators ask for serum sodium, serum chloride, and serum bicarbonate. Some calculators also include potassium, which produces a potassium value-based adjustment to the result.
The calculator performs an adjusted calculation that follows the basic chemistry of the blood. Sodium is the primary measured cation, while chloride and bicarbonate are principal measured anions. The remaining difference helps estimate unmeasured ions. This can be useful in blood test interpretation because the result may show a hidden acid load, a change in bicarbonate level, or an abnormal change in the sodium chloride balance.
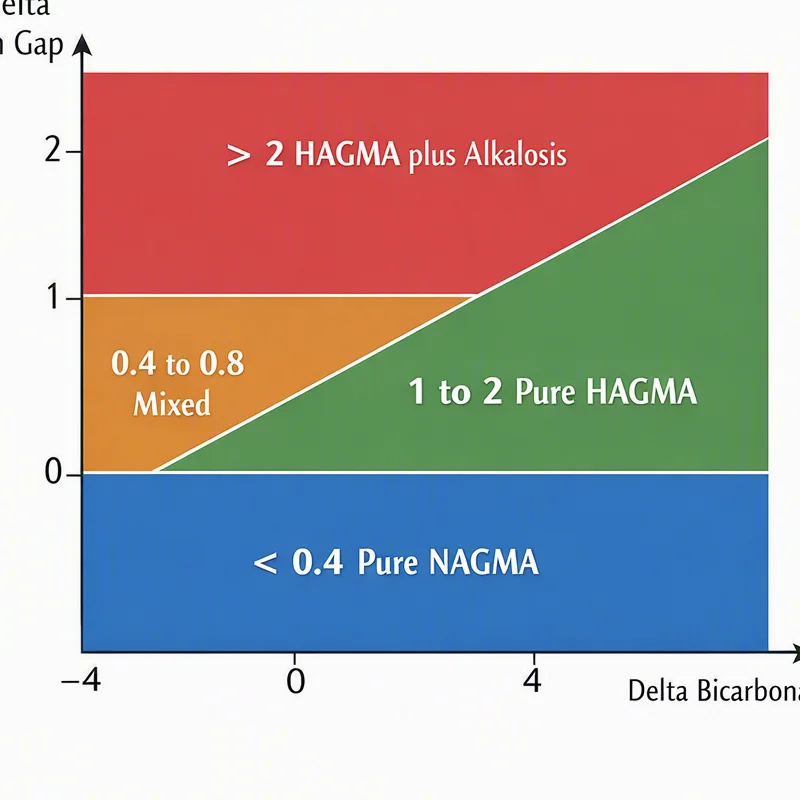
In practice, the calculator is a shortcut for understanding whether there is a gap in the measured ions that could indicate a specific problem. It does not take the place of a full clinical review, but it can be a useful first step in evaluating acid-base balance.
Formula for Anion Gap With and Without Potassium
There are 2 common methods to calculate the gap: a standard formula and a formula including potassium. This traditional method usually uses sodium, chloride, and bicarbonate. The potassium-inclusive approach adds serum potassium to the cation side of the equation.
One common traditional formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
A formula that includes potassium is:
Anion gap = (serum sodium + serum potassium) - (serum chloride + serum bicarbonate)
Both approaches can be valid, but they do not produce the same number. The potassium-added formula usually gives a slightly higher value because potassium is added to the cation total. For that reason, the normal range depends on which formula is used and on the laboratory reference range reported by the lab.
Most healthcare providers focus on whether the result falls within the expected reference interval for that specific method. A calculator should clearly identify whether it is using the traditional or potassium-inclusive approach, since misreading the formula can lead to confusion in clinical interpretation.
How to Input Blood Test Values Correctly
Precise results are based on entering the appropriate numbers for blood sodium, chloride, bicarbonate, and when applicable blood potassium. These values should come from the same specimen and same time period whenever possible, since mixed timing can alter the result.
Below are the key points to watch:
- Use the reported serum sodium value as given as listed. Input serum chloride from the same panel, not a estimated value. Enter the measured serum bicarbonate or total CO2 if that is what the lab shows. If the calculator includes blood potassium, use the serum potassium value from the same blood sample. Review units carefully so the inputs fit the calculator’s expected format.
Simple input errors can create a false low gap result or hide a true high anion gap. If the numbers seem inconsistent with the patient’s condition, confirm the laboratory values before drawing conclusions.
Interpreting a Elevated Anion Gap
A high anion gap usually indicates additional acids are contained in the blood. It is a classic pattern in metabolic acidosis and is commonly called high gap acidosis. The main causes include lactate acidosis, ketotic acidosis, renal failure, and poisonous alcohols or other toxic intake.
In lactic acidosis, https://anion-gap-results755.tearosediner.net/what-is-the-equation-for-anion-gap lactate builds up because of reduced oxygen delivery, shock, severe infection, or impaired metabolism. In ketotic acidosis, ketones increase due to insulin deficiency, starvation, or alcohol-related metabolic states. Renal insufficiency can reduce acid excretion and allow unmeasured acids to build up. Alcohol toxins such as methanol or ethylene glycol can also produce a pronounced gap because their metabolites are acidic.
When the gap is high, the central question is not only what the number is, but what it means in the overall medical context. Symptoms, medication history, kidney function, glucose, lactate, ketones, and toxicology may all matter. The anion gap is a clue, not the final diagnosis.
Understanding a Normal or Reduced Anion Gap
A normal anion gap does not eliminate acid-base disease. It may simply mean the body’s checked ions are balanced within the normal range. Certain types of metabolic acidosis, particularly when there is a rise in chloride, may show up as a normal gap rather than a high one.
A low anion gap is uncommon and requires careful review. One major cause is hypoalbuminemia, because albumin is a negatively charged protein that makes up part of the unmeasured anion pool. When albumin is low, the gap can decrease even if there is no major acid-base problem.
Other explanations include lab error, hyperchloremia, and paraproteinemia. Hyperchloremia can decrease the gap because chloride rises in relation to sodium and bicarbonate. Paraproteinemia, such as that seen in some plasma cell disorders, may also disrupt the expected balance of ions. Because of this, a low value should be reviewed against the full serum chemistry panel and repeated if needed.
In many cases, the most useful next step is to look for a measurement issue, verify albumin, and evaluate whether the result fits the patient’s condition. A low gap can be real, but it can also be a clue that the sample or calculation should be reviewed.
When Potassium Changes the Result
Including serum potassium in the formula can affect the final number, but the size of the change is often limited. The reason some calculators use a potassium-inclusive formula is tied to electroneutrality: potassium is a true cation and adds to the total positive charge in the blood.
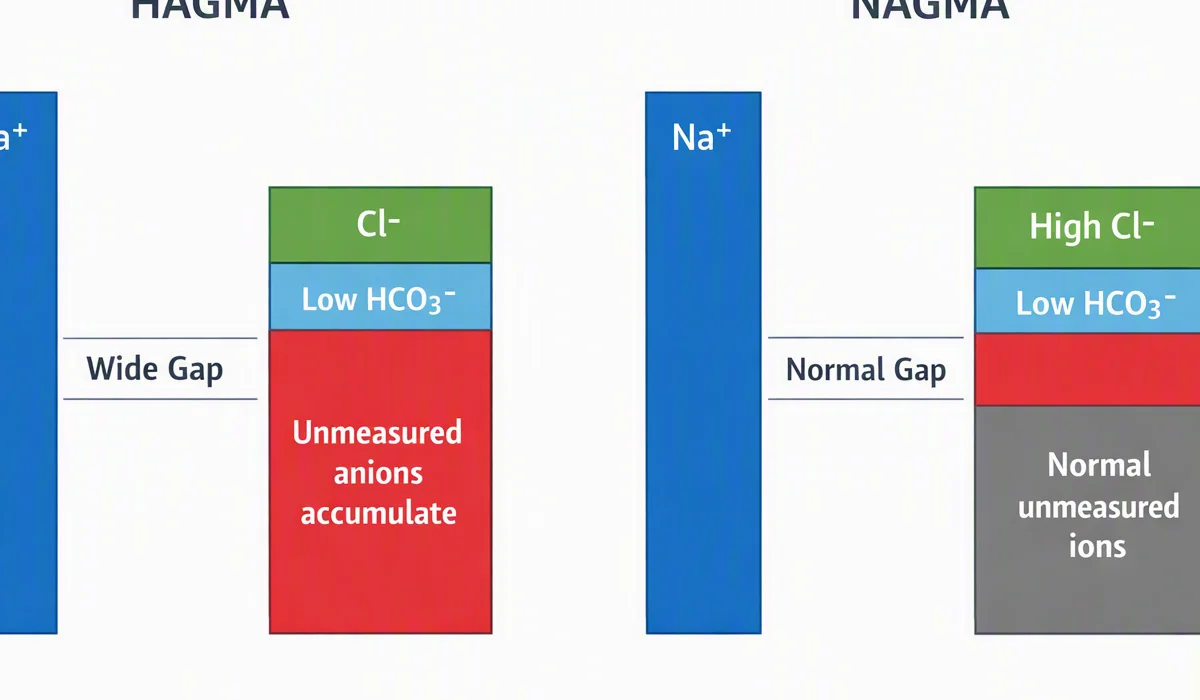
In routine practice, potassium may slightly increase the calculated gap, yet the clinical significance depends on how the result is being used. If the potassium value is normal, the difference between the standard and potassium-inclusive methods may not alter management. If potassium is markedly abnormal, the adjusted anion gap can provide a more complete picture of the electrolyte state.
That said, most clinicians still rely on the traditional approach because it is widely used in labs and textbooks. The potassium-inclusive method can be especially useful when a calculator is designed to reflect the full measured cation load and when you want a more detailed view of the patient’s electrolytes.
The practical point is this: potassium matters, but whether it affects the interpretation depends on the scenario. A calculator that accepts potassium can be a better choice for detailed review, while still requiring sound clinical interpretation.

Limits of Internet Anion Gap Calculators
Web-based calculators are handy, but they have significant limits. First, they use fixed reference limits that may not match every lab’s lab reference range. Different analyzers, cohorts, and formulas can produce different expected values. A number that looks abnormal in one setting may be acceptable in another.
In addition, many calculators do not adjust for albumin correction. Because low albumin can lower the anion gap, uncorrected results may underestimate the presence of an acid load. A proper review may require considering albumin as well as the measured electrolytes.
Third, blood gas and chemistry results are not interchangeable. A venous blood gas may help assess pH and bicarbonate, but its values are not identical to a standard chemistry panel. That difference matters when evaluating metabolic acidosis or a suspected acid-base disorder.
Lastly, calculators cannot replace clinical context. A result must be interpreted alongside symptoms, medications, kidney function, glucose, ketones, lactate, and other lab findings. The calculator is a resource for pattern recognition, not a standalone diagnosis.
Common Questions
What is an anion gap calculator used for?
An anion gap calculator is used for blood test interpretation when reviewing a serum chemistry panel. It helps estimate whether there is a hidden acid load, making it useful for detecting metabolic acidosis, especially high anion gap states. It can also help identify a normal anion gap or low anion gap that may need further review.
Should potassium be included in the anion gap formula?
Potassium is included in some formulas, especially the potassium-inclusive formula, but not all calculators use it. The traditional formula is more common, while the potassium version may better reflect total measured cations in certain cases. Whether to include potassium depends on the calculator design, lab method, and the purpose of the clinical interpretation.
How is a normal anion gap range?
The expected range depends on the calculation method and the testing facility. Some labs use a separate lab reference range for the traditional formula than for the potassium-inclusive method. Because of this, the most reliable approach is to check the result with the specific reference range reported by the laboratory rather than relying on one universal number.
What does a high anion gap mean?
A raised anion gap usually indicates acid buildup from unmeasured acids. Common causes include lactate buildup, ketone-related acidosis, renal impairment, and poisonous alcohols or other forms of toxin exposure. It is a finding that should be assessed with the rest of the electrolyte panel and the patient’s medical context.
Can a low anion gap be caused by lab error or low albumin?
Yes. A low anion gap can be caused by lab error or from low albumin, since the albumin level is a major unmeasured anion. Other causes include elevated chloride and abnormal protein levels. If the result is unexpected, it is reasonable to confirm the serum sodium, serum potassium, chloride level, and blood bicarbonate values and assess the full laboratory picture.