What the Anion Gap Is Measured
The anion gap is a computed value that helps clinicians understand electrolytes and overall acid-base balance. It is not directly measured on a blood test; instead, it is derived from standard lab values, particularly sodium, chloride, and bicarbonate. Because these numbers are part of the same chemistry panel, changes in one can influence the final result and its clinical significance.
At a basic level, the anion gap estimates the difference between the main positively charged and negatively charged ions in the blood. This makes it a useful diagnostic clue when assessing an unexpected result on a blood test. It can help reveal whether a patient may have a hidden acid-base problem, such as metabolic acidosis, or whether the issue is better explained by a change in serum levels of proteins or a possible measurement error.
Most often, clinicians review sodium, chloride, and bicarbonate together on the basic metabolic panel. These values are the backbone of many routine lab reviews. If sodium is low, the anion gap can look different even when the underlying chemistry has not changed much. That is why understanding the formula matters before drawing conclusions about the normal range or deciding whether an abnormal value is meaningful.
How the Anion Gap Calculator Operates
An Anion Gap Calculator is a useful utility that performs the same calculation clinicians use when assessing lab values. It uses the available serum bicarbonate, sodium, and chloride values to estimate the gap. Some calculators also ask for albumin or serum albumin because low protein levels can make the result appear falsely low and may require albumin correction.
The calculator is beneficial because it turns raw lab values into an reading aid. Rather than looking at sodium or chloride alone, it helps show how the numbers relate. This boosts result accuracy when evaluating an unexpected result and gives a better picture of the patient’s electrolyte balance.
In practical use, the calculator supports clinicians in distinguishing whether the pattern points toward a high anion gap or a low anion gap. A high value may indicate excess unmeasured acids, while a low value may suggest low albumin, a lab artifact, or less common causes such as paraproteins. The calculator does not replace judgment, but it supports faster, more structured lab interpretation.
Because the anion gap is calculated from routine chemistry data, even small shifts in sodium, chloride, or bicarbonate can change the outcome. That is why the calculator should always be used with the rest of the panel and the patient’s overall picture, not in isolation.
Can Reduced Na Change the Anion Gap?
Yes, hyponatremia can impact the anion gap, but the relationship is often nuanced. Since sodium is part of the formula, a decreased sodium value can alter the calculated result. However, a low sodium level does not automatically mean the anion gap is truly abnormal. The result may reflect the formula itself, the underlying cause of the sodium change, or a measurement error.
From a chemistry standpoint, the body maintains electroneutrality, meaning total positive and negative charges stay balanced. The anion gap is a way of gauging the portion of that balance not directly captured by the measured ions. If sodium falls, the calculation can shift, but whether that shift matters depends on the full lab pattern and clinical context.
For instance, if sodium is low because of fluid imbalance or a dilutional state, the gap may appear lower without a true change in acid-base status. If chloride or bicarbonate also changes, the effect may be more obvious. This is why clinicians should not interpret sodium in isolation. They use the entire panel to decide whether the result reflects a real disorder or a misleading number.
Low sodium can also coexist with conditions that cause a truly abnormal anion gap. In that setting, the sodium change is not the primary driver of the gap, but it may complicate the lab interpretation. The question is not simply whether sodium is low, but whether the low sodium is changing the calculation enough to obscure the underlying cause.
Typical Reasons for Low Sodium and an Unusual Anion Gap
Low sodium and an unusual anion gap often occur together because the same illness can influence fluid balance, kidney regulation of electrolytes, and acid formation. One common reason is dehydration. Even though dehydration is often associated with concentrated labs, severe fluid loss can alter sodium and other values in ways that make interpretation complicated, especially if bicarbonate also changes.
Kidney disease is another significant cause. As the kidneys cannot remove acids efficiently, the body may develop metabolic acidosis. In that setting, the anion gap may rise because unmeasured acids build up. Kidney dysfunction can also affect sodium regulation, making the lab pattern less straightforward.
SIADH, or syndrome of inappropriate antidiuretic hormone secretion, is a common cause of hyponatremia. In SIADH, water retention dilutes sodium, and the anion gap may look unusual depending on the rest of the chemistry panel. The anion gap itself may not be the main issue, but it can still help detect whether another acid-base disorder is present.
Some patients with low sodium and abnormal acid-base findings have a combined problem. For example:
- Low sodium with low bicarbonate may suggest a metabolic issue that needs closer review. Low sodium with elevated chloride may lower the anion gap or point away from a high-gap disorder. Kidney disease can contribute to both sodium imbalance and metabolic acidosis.
The key point is that low sodium may be a clue, not the diagnosis itself. A thorough review of electrolytes, serum bicarbonate, and other lab values is needed to determine the real diagnostic clue behind the pattern.
Reduced Anion Gap vs High Anion Gap
A low anion gap and a elevated anion gap suggest distinct possibilities. A high anion gap usually indicates too much acids in the blood, while a low anion gap often reflects decreased albumin, a lab issue, or uncommon disorders. That difference matters because the treatment approach depends on the magnitude of the change.
Albumin is one of the main reasons a low anion gap can occur. Because albumin carries a negative charge, low albumin can reduce the gap even when sodium, chloride, and bicarbonate are otherwise stable. This is why albumin correction is often necessary. A corrected anion gap may reveal that the result is less abnormal than it first appeared.
By contrast, a high anion gap often appears in conditions such as lactic acidosis and ketoacidosis. In lactic acidosis, the body retains lactate due to poor oxygen delivery or impaired metabolism. In ketoacidosis, ketones build up when the body uses fat for fuel. Both conditions can produce a high anion gap metabolic pattern that requires prompt attention.
Paraproteinemia can also lead to a low anion gap. Abnormal proteins in the blood may shift the charge balance enough to affect the calculation. This is not as common than low albumin, but it is clinically important when the result does not fit the rest of the labs.
Thinking in terms of low versus high anion gap helps focus the differential. It also keeps the clinician focused on the reference range, the surrounding chemistry, and the true clinical significance of the result rather than the number alone.
When a Low Anion Gap Is a Lab Artifact
Not all low anion gap indicates a medical problem. At times the result is a testing error or another lab artifact. That is why result review should cover the possibility of a specimen issue, especially when the number does not fit the patient’s symptoms or other findings.
One especially important artifacts is pseudohyponatremia. In this case, the measured sodium may look reduced than it actually is because of atypical sample composition, such as very high protein or lipid levels. If sodium is falsely low, the calculated anion gap may also seem misleading. This can produce a unclear pattern unless the sample is repeated or checked with a different method.
A different typical approach is retesting. If the result is unexpected, doing again the blood test may help confirm whether the issue is actual or due to chance variation, sample collection issues, or analyzer problems. It is especially vital when the lab pattern is out of sync with the patient’s status.
If sodium, chloride, or bicarbonate do not fit the clinical scenario, first check whether the value is reproducible before thinking a true acid-base disorder.
A low anion gap resulting from a lab artifact is typically identified when the sample is rechecked. This is why clinicians carefully monitor measurement error and how the specimen was obtained, processed, and analyzed.
How Clinicians Providers Read the Result
Doctors seldom read the anion gap on its own. They typically check the basic metabolic panel first, then order an arterial blood gas when needed to understand the acid-base picture more completely. Together, these tests provide a more complete view of the patient’s biochemistry and respiratory condition.
Interpretation often starts with reviewing sodium, chloride, bicarbonate, and serum albumin. If albumin is low, the anion gap may need albumin correction prior to interpretation. This is critical because a corrected anion gap may change the clinical picture from abnormal to almost normal.
The next step is considering the result into clinical context. Is the patient unwell, dehydrated, confused, short of breath, or showing signs of kidney dysfunction? Are there symptoms that suggest lactic acidosis or ketoacidosis? Does the pattern fit SIADH, or is there evidence of paraproteinemia? These considerations help determine whether the number represents a true disorder or a transient lab finding.
Clinicians also compare the result with prior labs when available. A sudden change may be more important than a mildly abnormal value that has remained stable. This method helps identify the underlying cause and supports better decision-making around further testing, treatment, or observation.
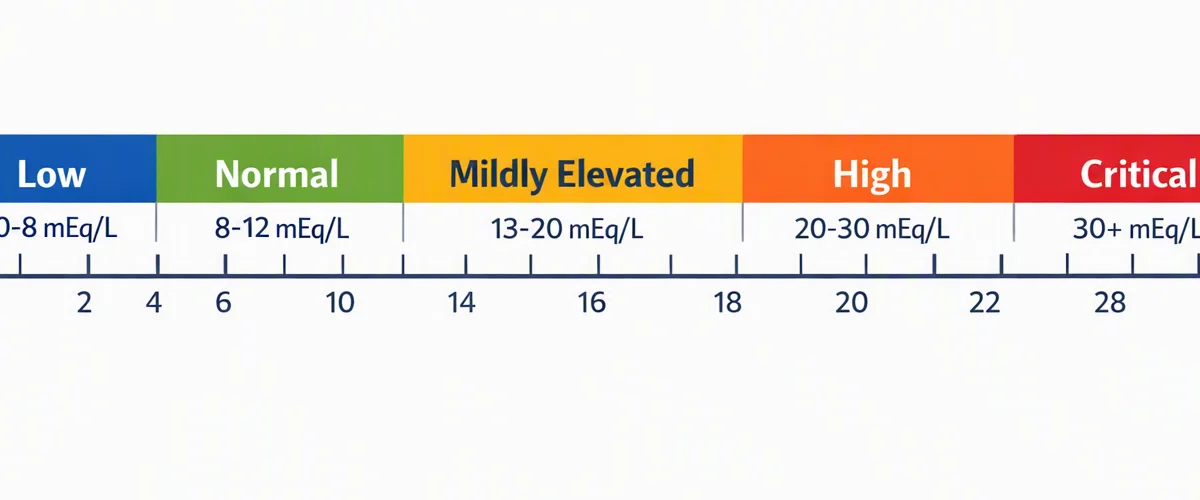
In short, the anion gap is a calculated value, but its interpretation is a clinical process. The best interpretation guide combines the calculator result with the patient’s symptoms, lab trend, and possible diagnosis.
When You Should Seek Medical Evaluation
Low sodium and an abnormal anion gap deserve medical evaluation when they are associated with alarming symptoms or when the result is severe. Mild changes may be monitored in some cases, but significant abnormalities can indicate a serious disorder that needs prompt attention.
Special concern comes with severe hyponatremia. If sodium is very low, the brain can be affected, leading to confusion, headache, nausea, weakness, or more serious neurologic symptoms. These findings should not be ignored, especially if the patient also has an abnormal anion gap or signs of metabolic illness.
Obtain prompt emergency care if abnormal labs occur along with fainting, seizures, severe confusion, trouble breathing, chest pain, or marked decline in alertness. These may indicate a life-threatening electrolyte or acid-base disturbance.
A low anion gap without symptoms may still need follow-up, especially if the result is persistent or paired with low albumin, kidney disease, or suspected paraproteinemia. Even if the cause is ultimately a lab artifact, confirmation matters because it prevents missed diagnoses and avoids unnecessary treatment.
The most prudent approach is to treat the Anion Gap Calculator as a guide, not a diagnosis on its own. If the result is unexpected, repeat the labs, review the basic metabolic panel, and discuss the findings with a clinician who can interpret them in context.
FAQ
Can low sodium lower the anion gap?
Yes, it can. Since sodium is included in the anion gap calculation, low sodium can lower the calculated value. However, the result may also reflect the underlying condition causing the sodium change or a lab artifact, so it should be interpreted with chloride, bicarbonate, and serum albumin.
Is hyponatremia a cause of low anion gap?
Hyponatremia may play a role in a low anion gap, but it does not always cause https://anion-gap-review155.swiftnestly.com/posts/anion-gap-calculator-for-standard-lab-assessment-and-analysis one by itself. The bigger question is why the sodium is low and whether other values, such as chloride and bicarbonate, support a true acid-base disorder.
What is the primary cause of a low anion gap?
Low serum albumin is one of the most common causes of a low anion gap. This is why albumin correction is essential. Next, lab artifact and measurement issues are also common explanations, especially when the result does not fit the clinical picture.
Can a low anion gap be due to a lab error?
Absolutely. A low anion gap can result from lab error, specimen concern, or pseudohyponatremia. Repeat testing is often the preferred first step when the value is unexpected or inconsistent with other lab findings.
When should I worry about abnormal sodium and anion gap results?
You should get medical evaluation if abnormal sodium and anion gap results occur with symptoms such as confusion, severe weakness, vomiting, shortness of breath, or signs of severe hyponatremia. Emergency care is critical if there are neurologic symptoms or a rapidly worsening condition.