What Is the Anion Gap?
The anion gap is a computed value used to assist evaluate acid-base status and electrolyte disturbance. It comes from routine blood chemistry and contrasts the main reported cations and anions in the blood, especially sodium and chloride, along with serum bicarbonate. Because not every charged particle is directly measured, the anion gap helps identify the existence of unmeasured anions and provides a useful diagnostic clue in metabolic acidosis.
In practical terms, the anion gap shows the difference between measured electrolytes in a serum chemistry panel. A typical anion gap formula uses sodium, chloride, and bicarbonate to estimate whether there are extra acids in the blood or whether bicarbonate has been lost. Clinicians use this result as part of the overall interpretation of a laboratory result, not as a standalone answer.
The value is especially useful when viewed in clinical context. A normal or elevated number does not by itself tell the whole story about severity, because the body may be in an acidotic state for different reasons. That is why the anion gap is often paired with other tests, including arterial blood gas testing, to understand the full metabolic disturbance.
How an Anion Gap Calculator Works
An anion gap calculator simplifies the computation from blood values, usually sodium, chloride, and serum bicarbonate. This makes it easier to quickly estimate whether the gap is within the expected reference range or whether it suggests high anion gap acidosis. The calculator is especially helpful when reviewing multiple lab results or tracking changes over time.
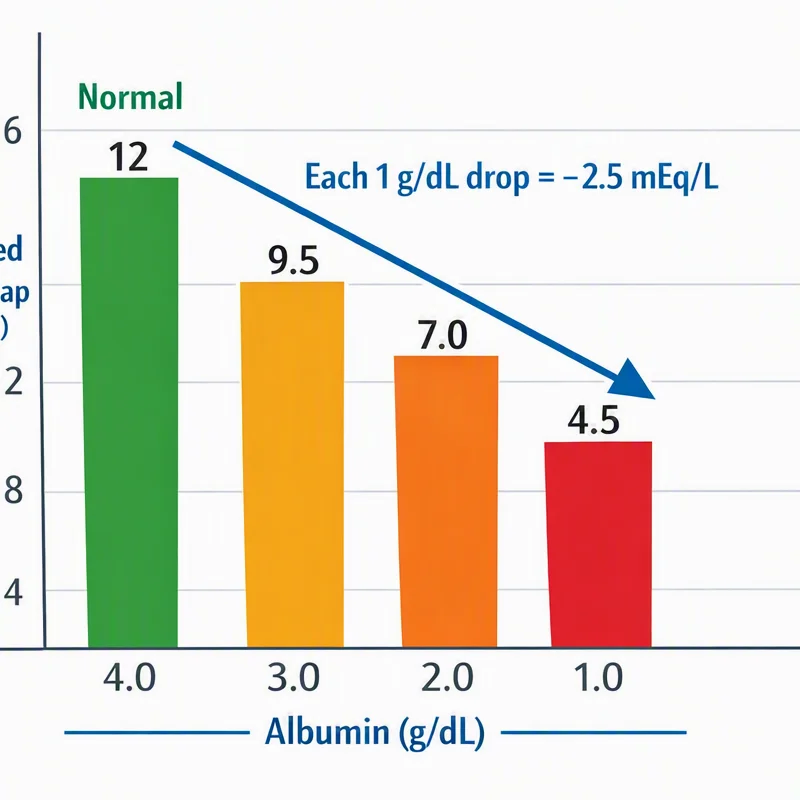
Many modern calculators also include albumin correction. Albumin is a negatively charged protein, so lower albumin can make the measured gap appear deceptively normal. An albumin-corrected anion gap modifies the result to better reflect true acid burden. This corrected gap can reveal hidden acid retention even when the uncorrected number seems unremarkable.
Because albumin changes the expected baseline, a normal value on the uncorrected calculation may not truly be normal. In other words, the corrected gap is often more useful than the raw number, especially when the blood chemistry suggests an acidotic state but the anion gap appears borderline. A good calculator supports better interpretation by accounting for these physiologic shifts.
Using an anion gap calculator does not replace judgment. It is a calculated value that must be considered alongside pH, base excess, serum electrolytes, and the overall pattern of the metabolic disturbance. The calculator is a tool, but the diagnosis comes from integrating the numbers with the patient’s condition.
Can Marked Acidosis Have a Normal Anion Gap?
Absolutely. Marked acidosis can absolutely occur with a unchanged anion gap. This is the main point many people miss. A normal gap does not rule out significant metabolic acidosis; it only indicates that the acid-base problem is not being driven by a large accumulation of unmeasured anions. In normal anion gap acidosis, the main problem is usually depletion of bicarbonate or a related shift in chloride.
This pattern is also called hyperchloremic acidosis because chloride increases to maintain electrical neutrality as bicarbonate falls. The result is marked acidemia in some cases, yet the anion gap stays within the expected range. The body is still acidic, but the chemistry pattern is distinct from high anion gap acidosis.
In severe cases, the serum bicarbonate may be very low, and the pH can be significantly reduced. The anion gap remains normal because the fall in bicarbonate is balanced by a rise in chloride. This is why a normal gap should never be interpreted as “no acidosis.” It simply points the clinician toward bicarbonate loss or chloride retention rather than excess unmeasured acids.
Understanding this distinction is essential in differential diagnosis. A patient with a normal anion gap and low bicarbonate may still be quite ill. The severity of the acidotic state is reflected more directly by pH and base deficit than by the gap itself.
Typical Causes of Normal Gap Metabolic Acidosis
Several conditions can cause normal anion gap acidosis. One of the most common is diarrhea, which leads to direct bicarbonate loss from the gastrointestinal tract. When bicarbonate is removed, chloride often climbs to preserve electroneutrality, producing a normal gap pattern.
Renal tubular acidosis is another major cause. In these disorders, the kidneys fail to appropriately process hydrogen ions or bicarbonate, resulting in persistent metabolic acidosis. Depending on the subtype, the blood may show low serum bicarbonate with normal or increased chloride. Even so, the anion gap can remain normal even when the acidosis is clinically significant.
Other frequent mechanisms involve either inadequate bicarbonate regeneration or excessive chloride exposure. Large-volume saline administration, for example, can contribute to chloride retention and a hyperchloremic pattern. This is not always dramatic on the surface, but it can meaningfully affect acid-base balance and blood chemistry.
These causes share a similar laboratory signature:
- Low serum bicarbonate Relatively high chloride Unremarkable or near-normal anion gap Signs of metabolic acidosis on blood gas testing
The pattern supports a careful diagnostic approach. Instead of searching first for lactate or ketoacidosis, clinicians should evaluate bicarbonate loss, chloride retention, and kidney-related causes when the gap is normal.
When a Typical Anion Gap Can Be Misinterpreted
A normal anion gap can be misread when other factors mask the true acid burden. One important issue is albumin. Because albumin is a key unmeasured anion, low albumin can depress the observed gap. Without albumin correction, a patient with serious acidemia may appear to have a normal value even though the corrected gap is actually elevated.
This matters particularly in a mixed acid-base disorder. For instance, a patient may have both lactic acidosis and bicarbonate loss, or ketoacidosis plus concurrent hyperchloremic acidosis. A single process may raise the gap while another drives it back toward normal. In that setting, the measured result can obscure the presence of high anion gap acidosis.
Lactate and ketoacidosis are classic causes of elevated gaps, but they may not always present in a straightforward, isolated pattern. If the body has already lost bicarbonate or received large amounts of chloride-containing fluid, the gap may look normal despite a serious metabolic problem. That is why the calculated number must be viewed with the full clinical picture.
In short, a normal gap can represent:
- Actual normal anion gap acidosis A combined disorder that offsets the numbers Hypoalbuminemia concealing an elevated corrected gap A timing issue, where lab values change as the condition evolves
So the normal result is not the conclusion of the workup. It is a diagnostic clue that should be considered against the patient’s symptoms, serum electrolytes, and other studies.
How to Understand Values in Medical Context
Interpreting the anion gap accurately requires considering several test results. The arterial blood gas provides key information about pH and ventilation, while the serum chemistry panel displays the underlying electrolyte pattern. In combination, they indicate whether the patient has acidemia, the extent of the problem, and whether compensation is present.
The pH shows you whether the blood is acidotic or alkalemic. The base excess helps measure the degree of metabolic abnormality, while serum bicarbonate reflects the buffering status directly. If pH is low and bicarbonate is low, the patient is definitely in a metabolic acidosis, even if the anion gap is normal.
Clinical context matters because the same laboratory result can mean different interpretations depending on the situation. A normal gap in a patient with diarrhea may fit bicarbonate loss. In someone with diabetic symptoms, the same result may suggest a mixed acid-base disorder or a corrected gap that should be reviewed carefully. The interpretation https://anion-gap-widget025.tearosediner.net/can-hypoxia-elevate-the-anion-gap is never just arithmetic; it is a clinical judgment.
Key considerations to consider include:
- Check the albumin level and evaluate the corrected gap Examine the serum chemistry panel for chloride and bicarbonate trends Verify the acid-base status with arterial blood gas results Assess for evidence of compensation or a mixed disorder Rely on pH and base excess to assess severity, not only the anion gap
The best approach is to treat the anion gap as one part of a broader evaluation. It helps guide the differential diagnosis, but it does not substitute for a full acid-base assessment.
Frequently Asked Questions
Is the anion gap ever normal in severe acidosis?
Yes. Severe acidosis can occur with a normal anion gap, especially in normal anion gap acidosis. This usually happens as bicarbonate is depleted or chloride rises to balance the decrease in bicarbonate. A patient can remain significantly acidotic even if the gap stays in the normal range.
What causes normal anion gap metabolic acidosis?
Typical causes include diarrhea, renal tubular acidosis, and other forms of bicarbonate loss. Retained chloride can likewise cause this pattern. These conditions typically create hyperchloremic acidosis with a normal or near-normal anion gap.
Why does albumin matter when interpreting the anion gap?
Albumin is a key unmeasured anion, so low albumin may make the anion gap appear falsely normal. Albumin correction helps uncover the true corrected gap. This matters most when the clinical presentation suggests more severe metabolic acidosis than the initial number indicates.
Is a normal anion gap possible in ketoacidosis or lactic acidosis?
Yes, they can. Although ketoacidosis and elevated lactate usually cause high anion gap acidosis, the gap may appear normal in a mixed acid-base disorder or if hypoalbuminemia is present. Earlier bicarbonate loss or chloride loading may also obscure the expected rise.
How is an anion gap calculator used alongside blood gas results?
An Anion Gap Calculator should be used in combination with arterial blood gas results, not rather than them. The calculator helps determine whether the pattern matches normal or high anion gap acidosis, while the blood gas displays pH, base excess, and overall severity. Together, they offer a more complete interpretation of the acid-base disturbance.