What Is Hyperchloremic Acidosis?
This condition is a form of metabolic acidosis in which the body has too much acid relative to base, but the anion gap stays within the normal range. It is also called normal anion gap metabolic acidosis or non-anion gap acidosis. The key lab pattern is a decrease in bicarbonate paired with a rise in chloride, which helps preserve electroneutrality.
This is important because it points to the mechanism of the disorder. Instead of accumulating unmeasured acids, the body often sheds bicarbonate or swaps it for chloride. That shift changes serum bicarbonate and serum chloride while leaving the calculated gap relatively unchanged. For that reason, hyperchloremic acidosis is more of a indicator about the type of acid-base problem than a single disease.
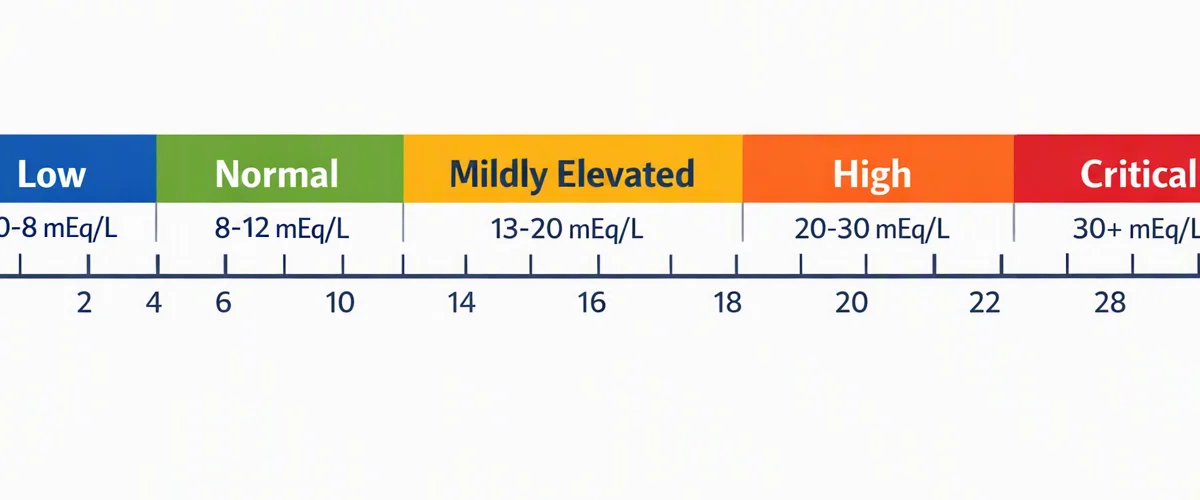
Clinically, hyperchloremic acidosis reflects an acid-base balance problem caused by an electrolyte imbalance. The blood chemistry may show reduced bicarbonate, increased chloride, and a normal calculated gap, which is why careful clinical interpretation is essential. It is a common diagnostic clue when reviewing lab values and assessing systemic acidemia.
What exactly is the Anion Gap and How Is It Measured?
The anion gap is a formula used to anion gap clinical significance estimate the difference between the main measured positive ions and negatively charged ions in blood. In everyday practice, an anion gap calculator helps quickly handle this step and reduce arithmetic errors. The typical anion gap formula uses sodium, chloride, and bicarbonate values from the metabolic panel.
The simple equation of the calculation is:
Anion gap = sodium - (chloride + bicarbonate)
Because sodium is the major measured cation and chloride and bicarbonate are the principal measured anions, the gap reflects the amount of unmeasured charged particles in serum. A normal result suggests that the acid-base disturbance may be due to bicarbonate loss or chloride gain rather than an increase in unmeasured acids.
An anion gap calculator is particularly useful when reviewing serum electrolytes alongside the remainder of the chemistry panel. It can support efficient lab interpretation and identify whether the pattern fits a normal gap disorder or a gap metabolic acidosis. That distinction is methanol AG patterns central to clinical interpretation because it shifts the differential diagnosis.
In practice, the anion gap is influenced by multiple factors, including albumin, which is a principal unmeasured anion. Low albumin can make the gap appear falsely normal, so the raw number should never be interpreted in isolation.
Reasons Why Hyperchloremic Acidosis Usually Has a Normal Anion Gap
This condition commonly produces a unchanged anion gap because the fall in bicarbonate is matched by a gain in chloride. This balance preserves electroneutrality. When bicarbonate is lost, chloride often increases to maintain balance among the measured ions, so the calculated gap does not increase much.
This is the key difference between hyperchloremic acidosis and high gap metabolic acidosis. In high-gap states, the body retains unmeasured acids, which increases the gap. In hyperchloremic states, the issue is often bicarbonate loss or chloride replacement, so the problem shows up as a change in measured electrolytes rather than a buildup of hidden anions.
Put another way, the body may be losing base, not gaining a large amount of new acid. That is why the lab pattern is often called normal anion gap metabolic acidosis. The chemistry pattern is still a true metabolic acidosis, but the chloride rise counteracts the bicarbonate decline.
This relationship is useful when examining serum chloride, serum sodium, and serum bicarbonate. If the bicarbonate is low and chloride is elevated, the problem is likely a non-anion gap process. The pattern can also reflect metabolic compensation in some settings, but persistent bicarbonate loss generally indicates a primary disorder.
Common Causes of Hyperchloremic Acidosis
A number of conditions can lead to hyperchloremic acidosis, and they often share a common theme: reduced bicarbonate, impaired renal acid handling, or chloride loading. Identifying the cause helps with targeted treatment and improves acid-base balance.
- Diarrhea: Loss of bicarbonate-rich digestive fluids can result in a non-anion gap acidosis. Renal tubular acidosis: The kidneys cannot adequately remove acid or retain bicarbonate, leading to renal acid excretion problems. Normal saline: Substantial fluid administration can raise chloride and lower bicarbonate, causing a hyperchloremic pattern. Kidney disease: Reduced renal function can disrupt acid regulation and contribute to electrolyte shifts.
Diarrhea is a classic cause because gastrointestinal bicarbonate loss can be substantial. The result is a low bicarbonate level with a compensatory rise in chloride. This is a straightforward example of bicarbonate loss driving a non-anion gap acidosis.
Renal tubular acidosis is another important cause. In this category of disorders, the kidneys fail to acidify urine appropriately or preserve bicarbonate effectively. The disorder may be a key clue in a patient with chronic electrolyte imbalance, persistent low bicarbonate, and a normal anion gap.
Normal saline can also play a role, especially when given in large amounts. Because saline contains a large chloride load, it can cause a apparent increase in serum chloride and a fall in bicarbonate. This is a clear illustration of how treatment itself may affect blood chemistry and the acid-base picture.
Kidney disease may cause hyperchloremic acidosis as renal function declines and acid handling becomes weaker. In some cases, the pattern reflects reduced ammonium excretion, ongoing acid load, and impaired buffering. Reviewing the full clinical context and lab values is essential for correct diagnosis.
Interpreting the Anion Gap in Acid-Base Imbalances
Understanding the anion gap requires more than looking at a single result. The result should be considered alongside pH, bicarbonate, chloride, albumin, and the overall acid-base disorder. A normal gap does not necessarily mean the problem is minor, and a high gap does not necessarily mean the cause is obvious.
Albumin matters because it is a major unmeasured anion. When albumin is low, the measured gap may underestimate the true burden of unmeasured acids. That is why a corrected anion gap is often needed. Correction helps avoid missing a hidden high-gap process in a patient whose albumin is reduced.
The delta gap is another important tool. It helps identify whether more than one acid-base process is present by comparing the rise in anion gap with the fall in bicarbonate. If the numbers do not match expected patterns, a mixed acid-base disorder may be present.
For example, a patient can have a normal anion gap acidosis and a separate high-gap process at the same time. In such cases, the apparent pattern may be deceptive unless corrected for albumin and evaluated with the delta gap. This is where careful lab interpretation becomes essential.
Useful interpretation steps include:
- Assess the raw anion gap and compare it with the expected range. Review albumin and calculate the corrected anion gap if needed. Look at the relationship between bicarbonate and chloride. Use the delta gap to screen for a mixed disorder. Compare the pattern with the clinical picture and underlying acid-base disorder.
This approach supports more accurate clinical interpretation and helps distinguish a pure hyperchloremic process from a more complex acid-base disturbance.
When a Increased Anion Gap and Chloride elevation Can Appear together
A raised anion gap and hyperchloremia can occur together when more than one process is occurring at once. This is a classic mixed acid-base disorder. The patient may have a high-gap process from one cause and a hyperchloremic component from another.
Common examples include lactic acidosis, ketoacidosis, and toxic ingestion. These conditions often raise unmeasured acids, leading to a elevated anion gap. At the same time, chloride may increase or bicarbonate may decrease further, producing a second pattern that can mask the overall picture.
For instance, a patient with ketoacidosis may receive large volumes of normal saline, which can contribute a hyperchloremic component to the already existing high-gap disorder. Similarly, lactic acidosis may appear together with chloride retention or bicarbonate loss, making the lab values more challenging to interpret.
Toxic ingestion can also produce mixed patterns depending on the substance and the timing of presentation. Some toxins cause high-gap acidosis directly, while treatment or fluid shifts may later introduce a hyperchloremic component. This is why looking only at the anion gap without the rest of the blood chemistry can miss important context.
The delta gap is especially useful here because it helps reveal whether the bicarbonate drop is more pronounced or less severe than expected from the rise in anion gap alone. When the numbers do not fit a single disorder, mixed physiology should be strongly thought about.
How an Anion Gap Calculator Supports Clinically
A anion gap calculator is a useful tool for fast review of serum electrolytes. It supports bedside decision-making by helping clinicians compare sodium, chloride, and bicarbonate values promptly. This makes it easier to recognize whether a patient has hyperchloremic acidosis, a high-gap disorder, or a mixed pattern.
In daily practice, the calculator helps with:
- Rapid screening of electrolytes during evaluation of acidemia. Improved lab interpretation when bicarbonate is low. Tracking serum bicarbonate changes over time. Aiding review of serum chemistry panels in complex cases. Seeing when chloride rise suggests a non-anion gap process.
The tool is especially helpful when paired with clinical context. If the patient has diarrhea, renal tubular acidosis, recent saline resuscitation, or kidney disease, the anion gap result may help confirm the likely mechanism. If the gap is unexpectedly high or normal in the setting of serious illness, that may be a signal to look for a hidden mixed disorder.
A calculator does not replace judgment, but it strengthens it. By combining the anion gap with albumin correction, bicarbonate review, and delta gap analysis, clinicians can interpret blood chemistry with greater confidence and identify the source of the acid-base imbalance.
Used well, the anion gap calculator becomes more than a math tool. It becomes a diagnostic aid that supports better recognition of electrolyte patterns, quicker clinical interpretation, and more targeted management of systemic acidemia.
Frequently Asked Questions
How is hyperchloremic acidosis different from high anion gap acidosis?
Hyperchloremic acidosis is usually a normal anion gap metabolic acidosis caused by bicarbonate loss or chloride gain, while high anion gap acidosis reflects accumulation of unmeasured acids. In hyperchloremic acidosis, chloride goes up as bicarbonate goes down, whereas in high anion gap states the gap increases because of acids such as lactate or ketones.
How come hyperchloremic acidosis usually have a normal anion gap?
It typically has a normal anion gap because the decrease in bicarbonate is offset by an increase in chloride, preserving electroneutrality. Since the measured ions shift in opposite directions, the calculated anion gap often stays within the normal range.
Is it possible for normal saline cause hyperchloremic acidosis?
It can. Substantial amounts of normal saline can raise chloride and dilute bicarbonate, which leads to hyperchloremic acidosis. This is a common explanation for non-anion gap acidosis in patients receiving large fluid resuscitation.
How do you compute and adjust the anion gap with respect to albumin?
You compute the anion gap by subtracting the sum of chloride and bicarbonate from sodium. To adjust for albumin, you raise the result when albumin is low because low albumin can make the gap seem falsely normal. This albumin-corrected anion gap offers a better estimate of hidden unmeasured acids.
What conditions commonly cause hyperchloremic acidosis?
Common causes include diarrhea, renal tubular acidosis, normal saline administration, and kidney disease. These conditions often cause bicarbonate loss, reduced renal acid excretion, or chloride loading, each of which can produce a normal anion gap pattern.