Why the Anion Gap Evaluates
The anion gap is a helpful clinical concept for understanding electrolytes and how they relate to acid-base balance. It helps clinicians and students detect patterns that may suggest a metabolic acidosis or a different acid-base disorder. Rather than assessing every charged particle in the blood, the anion gap calculates the difference between major measured cations and anions in blood chemistry.
In everyday terms, the anion gap reflects the amount of unmeasured anions in the serum. These may include substances such as organic acids and other negatively charged components that are not listed directly on a routine panel. Because the body relies on a tightly regulated buffer system, a change in this value can suggest a metabolic disturbance that may be clinically significant.
An anion gap calculator is a straightforward diagnostic aid that assists clarify a laboratory result into a more meaningful interpretation. It is especially helpful when reviewing a basic metabolic panel or an arterial blood gas, since those tests often provide the data needed for result analysis.
How to Use the Anion Gap Calculator Operates
This calculator uses three key inputs: sodium, chloride, and bicarbonate. They are often listed as serum sodium, serum chloride, and serum bicarbonate on routine laboratory reports. The calculation formula is straightforward and allows quick screening for an electrolyte imbalance.
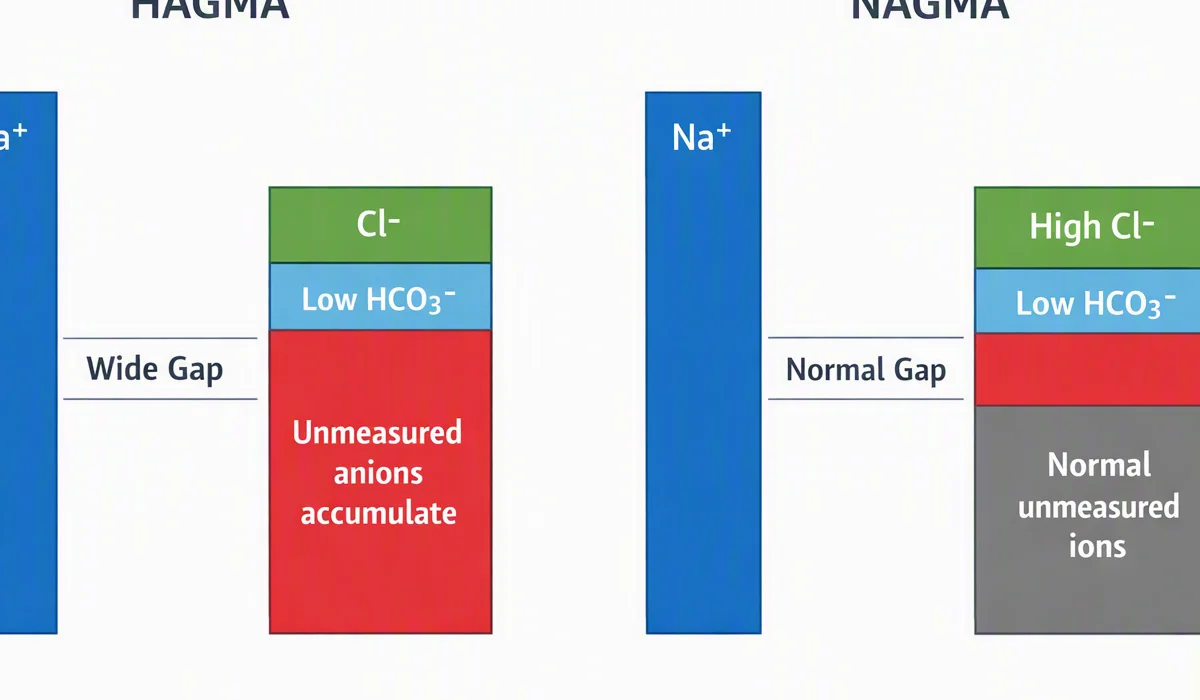
The core idea is that sodium represents the major measured cation, while chloride and bicarbonate represent the primary measured anions. The calculator estimates the difference between them to show whether there is an anion deficit or surplus of unmeasured acids.
As an example, if sodium is 140, chloride is 102, and bicarbonate is 24, the result is 140 minus 102 minus 24, which equals 14. That result may be within a typical reference range, depending on the laboratory’s reference interval. The exact meaning depends on the complete clinical context and the patient’s other test results.
This turns the calculator a useful way to support clinical decision support, especially when evaluating a suspected acid-base imbalance. It does not replace clinical judgment, but it can rapidly guide the next step in result analysis.
Anion Gap Equation & Common Variations
The standard anion gap formula reads:
Na minus Cl and HCO3
Shown in its standard format, this means:
Anion Gap = Na - chloride plus bicarbonate
This formula is the foundation of most calculator tools. Some systems may also display a variation that includes potassium, but most everyday interpretations use the more basic version above because it is simpler to use and still clinically useful.
Another important form is albumin correction. Because albumin is a key unmeasured anion, a low albumin level can make the anion gap appear falsely low or normal. In those cases, the corrected anion gap provides a more accurate estimate of the true acid-base status.
A normal anion gap usually suggests that any acidosis present may be due to bicarbonate loss with a compensatory chloride increase, while an elevated anion gap suggests accumulation of unmeasured acids. The distinction is important because it alters the differential diagnosis and the next clinical steps.
Reading High, Normal, and Low Anion Gap Results
A raised anion gap means there are more unmeasured anions than expected. This often suggests an acid load in the blood and may be associated with metabolic acidosis. In interpretation, the exact cutoff depends on the laboratory reference interval, so it is best to compare the result to the lab’s own range rather than assume one universal number.
A normal anion gap does not always mean everything is fine. It may indicate a specific type of metabolic acidosis in which bicarbonate falls but chloride rises enough to keep the gap stable. That pattern is often called hyperchloremic acidosis, and it can still be a meaningful finding in the right context.
A low anion gap is less common but can be important. It may reflect low albumin, measurement issues, or unusual laboratory patterns. In some cases, it may be related to a clinically meaningful disorder rather than simple variation.
Clinical interpretation should always consider symptoms, medications, kidney function, and the broader blood chemistry picture. The anion gap is best viewed as a screening tool that points toward likely causes rather than as a final diagnosis.
Why Low Sodium, Chloride, or Bicarbonate Influence in the Computation
The anion gap calculation depends on the balance among sodium, chloride, and bicarbonate, so abnormalities in any one of these can influence the final number. Understanding how each value changes the result helps explain why the calculator is important for detecting an electrolyte imbalance.
Hyponatremia, or low sodium, can decrease the anion gap because sodium is the key measured cation in the formula. If sodium drops, the calculated gap may fall even if the underlying acid-base problem has not changed much. That is why the raw number must be interpreted in context.
Hyperchloremia, or high chloride, can also reduce the gap because chloride is subtracted in the calculation. This pattern is often seen when bicarbonate is lost and chloride rises in compensation. In that situation, the normal anion gap may remain unchanged even though an acid-base disorder is present.
Hypobicarbonatemia, or low bicarbonate, often raises concern for acidosis. Since bicarbonate is subtracted in the formula, a lower bicarbonate value can increase the anion gap if chloride does not rise enough to offset the change. This is one reason the calculator is so valuable in recognizing metabolic acidosis early.
These shifts illustrate how the anion gap is a mathematical summary of underlying physiology. A single laboratory result can reflect a broader metabolic disturbance, and the calculator helps make that pattern easier to identify.
Typical Causes of an Unusual Anion Gap
An unexpected anion gap often suggests one of several common causes. The most important causes of a high anion gap include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each of these conditions increases unmeasured acids or limits the https://anion-gap-chart421.talesignal.com/posts/anion-gap-calculator-for-evaluating-acidic-metabolic-states body’s ability to clear them.
Lactic acidosis occurs when lactate accumulates, often because tissues are not receiving enough oxygen or because metabolism is otherwise stressed. It is a common reason for elevated gap results in acute illness.
Ketoacidosis can develop when ketone bodies build up, such as in uncontrolled diabetes, prolonged fasting, or other states of accelerated fat breakdown. Ketones contribute unmeasured anions that raise the gap higher.
Renal failure can cause accumulation of acids that the kidneys would normally excrete. As kidney function worsens, the body may accumulate organic acids and other metabolites that increase the gap.
Toxic alcohols are also notable because they can be metabolized into acidic compounds. This makes the anion gap a helpful clue in urgent evaluation, especially when the history is unclear.
A normal or low value can also be important, but it should not distract from the broader clinical picture. The calculator is one part of a structured result analysis, not the entire diagnosis.
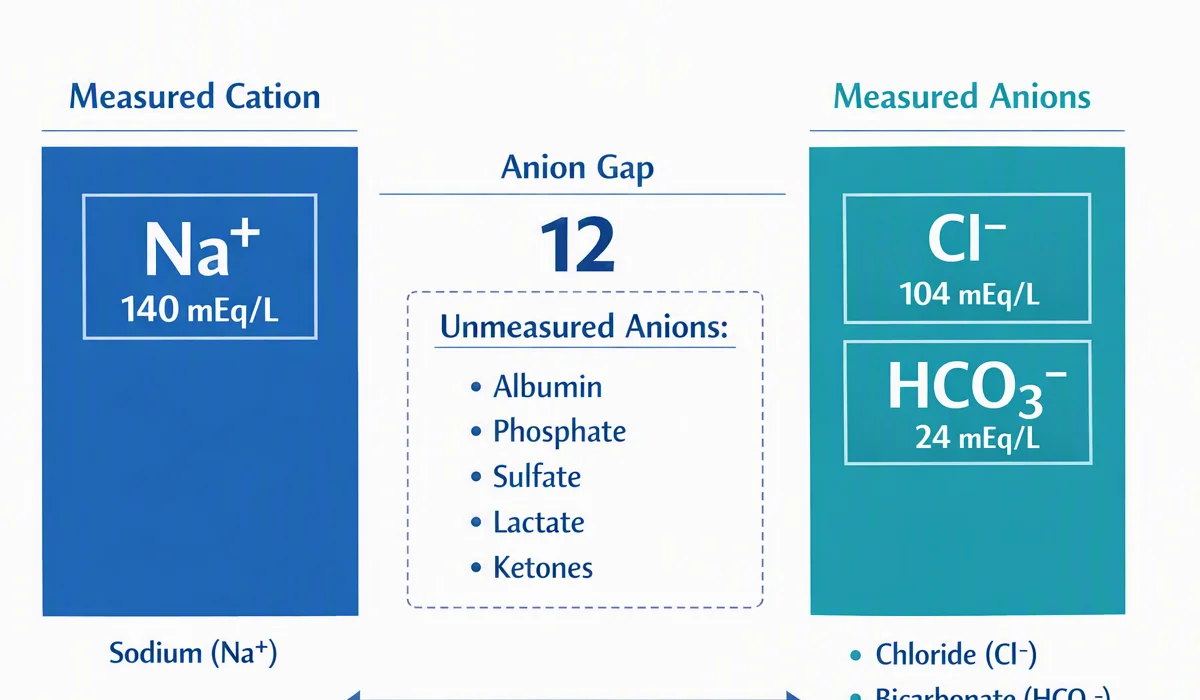
When to Use an Anion Gap Calculator in Clinical Practice
An anion gap calculator is most useful when evaluating a basic metabolic panel or an arterial blood gas in a patient with likely acid-base abnormalities. It is especially valuable in a metabolic acidosis workup, where the goal is to determine whether the acidosis is due to unmeasured acids or to bicarbonate loss with chloride retention.
Clinicians often use the calculator as a rapid screening tool when reviewing a patient with abnormal breathing, altered mental status, dehydration, kidney dysfunction, or unexplained illness. In those settings, the number can guide whether further testing is needed.
The calculator also provides clinical decision support in routine settings. For example, if a lab report shows low bicarbonate, the next question is whether the anion gap is elevated, normal, or low. That distinction helps narrow the differential diagnosis and decide what additional testing is appropriate.
In short, the calculator is useful whenever sodium, chloride, and bicarbonate are available and there is concern for an acid-base disorder. It is a quick way to turn raw lab data into a meaningful clinical pattern.
Constraints and Validity Considerations
Even though the calculator is handy, it has drawbacks. One important issue is albumin. Since albumin carries a negative charge, low levels can decrease the measured gap even when an underlying acid-base problem exists. This is why albumin correction may be needed for greater accuracy.
Another concern is the lab reference range. Separate laboratories may use slightly different methods and calibration standards, so the same result might be interpreted differently depending on the assay. Be sure to compare the number to the local reference interval rather than assuming a single universal cutoff.
Measurement error can also affect the result. Slight variation in sodium, chloride, or bicarbonate values may shift the final number enough to change interpretation, especially when the result is near the upper or lower end of normal. This is one reason a single result should not be overread without the clinical context.
If albumin is low, the corrected anion gap may better reflect the true balance of measured and unmeasured anions. This adjusted value can improve interpretation and lessen the chance of missing a clinically important acid-base disorder.
Given these limitations, the anion gap should be used as part of a broader assessment, not as a standalone conclusion. It is most accurate when combined with symptoms, medication review, kidney function, and other blood chemistry findings.
FAQ
How do you calculate the anion gap using sodium, chloride, and bicarbonate?
Use the anion gap formula: sodium minus the sum of chloride and bicarbonate. In brief, it is Na minus Cl and HCO3, or more clearly, anion gap = sodium - (chloride + bicarbonate). This calculation is the basis of most calculator tools and provides a quick estimate of the difference between measured cations and anions.
How to define a normal anion gap value?
The normal range depends on the laboratory’s reference range and testing methods. Different labs may show slightly different values, so the best method is to compare the result with the local reference interval. In general, a result within that range suggests a normal anion gap, but interpretation still depends on the rest of the clinical picture.
Why does albumin affect the anion gap?
Albumin is a major unmeasured anion in blood. When albumin is low, the measured anion gap may appear lower than expected even if an acid-base problem is present. That is why albumin correction is important. A corrected value can provide a more accurate picture of the patient’s true acid-base status.
What causes a high anion gap?
A high anion gap is commonly caused by lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These conditions increase unmeasured acids in the blood and often signal a significant metabolic disturbance. The exact cause depends on the full clinical context, symptoms, and other laboratory findings.
Can a low anion gap be clinically important?
Yes. A low anion gap can be clinically important, especially if it reflects low albumin, an electrolyte imbalance, or a laboratory issue that needs follow-up. It may also point to unusual chemistry that deserves closer review. Even though it is less common than a high result, it should not be ignored if the interpretation does not fit the rest of the patient’s blood chemistry.