What Is the Anion Gap?
The anion gap is a computed value that aids clinicians assess serum electrolytes and identify signs of acid-base disorder. It compares the main measured cations and anions in blood, especially serum sodium and serum chloride, with serum bicarbonate as part of routine serum chemistry review.
Although the name suggests a literal gap, the value represents the difference between regularly measured positively charged and negatively charged particles. That difference reflects unmeasured anions in the blood, which can increase during particular cases of metabolic acidosis. In practice, the anion gap is a fast screening tool for understanding acid-base balance and identifying a possible metabolic derangement.
Because the body relies on a closely regulated buffer system, even modest changes in electrolytes can signal important disease. A widened anion gap may point toward excess acids such as lactate or ketones, while a normal gap with low bicarbonate often suggests bicarbonate loss or a chloride shift. This is why the anion gap is so useful in diagnostic evaluation.
How the Anion Gap Calculator Works
An anion gap calculator simplifies the calculation formula used to calculate the gap between measured cations and anions. The basic version takes sodium, chloride, and bicarbonate values from a lab report. Most calculators are designed to make clinical interpretation faster and more reliable than doing the math manually.
The standard formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This formula illustrates the relationship between the major measured ions in the bloodstream. If the result is above normal than the expected reference interval, it suggests the presence of acids that are not directly measured on the panel. These may include lactate, ketones, sulfates, or other organic acids.
Many modern calculators also include albumin correction. That matters because serum albumin is a major unmeasured anion. If albumin is low, the calculated anion gap can appear incorrectly normal even when clinically important acidosis is present. Using an adjusted result improves severity assessment and helps avoid missing a hidden problem.
In other words, the calculator does more than produce a number. It helps connect the number to the likely physiology behind it, supporting a clearer read on systemic acidosis and overall acid-base status.
How to Calculate the Anion Gap Step by Step
To work out the anion gap manually, use values from a blood chemistry panel or an electrolyte panel. The key values are Na+, Cl-, and HCO3-. Once you have them, apply the formula directly.
Follow these steps:
- Find the serum sodium value, written as Na+. Identify the serum chloride value, written as Cl-. Find the serum bicarbonate value, written as HCO3-. Sum chloride and bicarbonate together. Take away that total from sodium.
As an example, if sodium is 140, chloride is 102, and bicarbonate is 22, then 140 - (102 + 22) = 16. This result may be above the usual reference interval, depending on the laboratory’s method and reporting style.
It is important to use the exact values from the lab, because small differences can change the interpretation. A blood chemistry panel is often enough to calculate the anion gap, but the context matters. If there are symptoms or additional abnormalities, the anion gap should be interpreted as part of a broader clinical assessment.
When the result is unexpectedly high or low, verify units, confirm the lab source, and review other signs of electrolyte imbalance. The calculator is a tool, not a diagnosis by anion gap clinical significance itself.
Reading a Increased Anion Gap Acidosis
A high result on anion gap calculator often indicates high anion gap metabolic acidosis. This means acidic compounds have accumulated in the blood, using up bicarbonate and raising unmeasured anions. Common causes include lactic acidosis, ketoacidosis, and uremia.
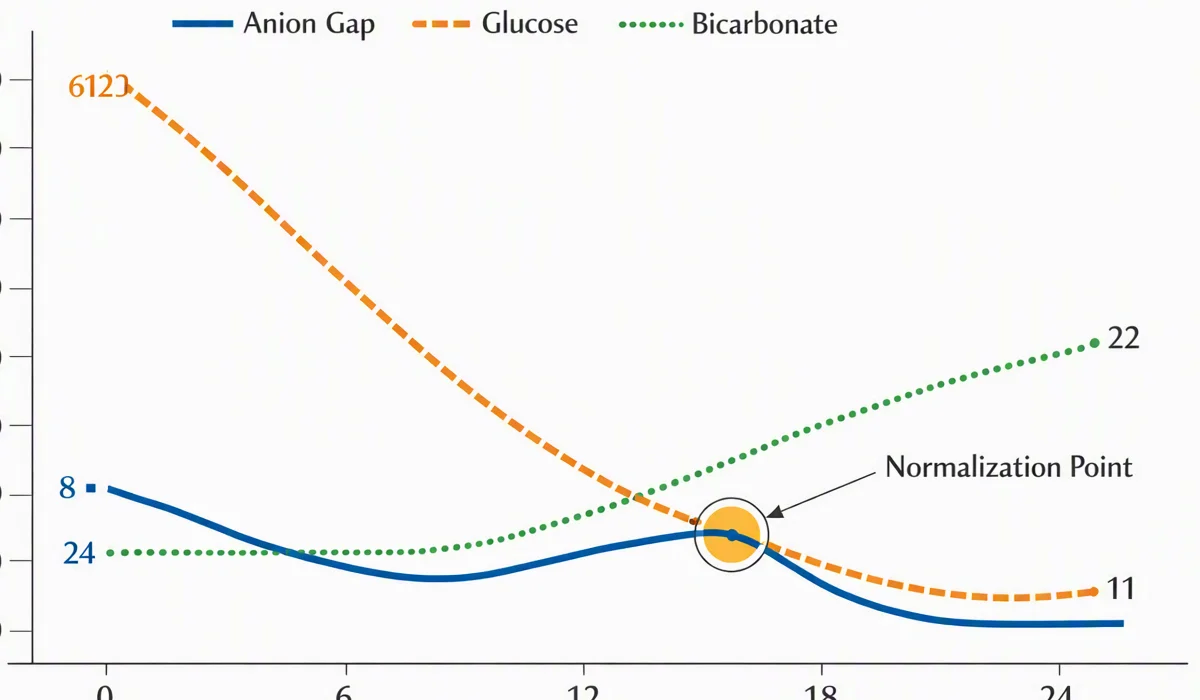
In lactic acidosis, lactate builds up when tissues are under stress or oxygen delivery is limited. This can happen during shock, severe infection, poor perfusion, or intense physiologic stress. Lactate is an organic acid, so it contributes to the rise in unmeasured anions.
Ketoacidosis occurs when the body breaks down fat for fuel and produces ketone acids. This is classically seen in diabetes, but it can also occur with starvation or alcohol use. The low bicarbonate and increased acids create a typical pattern of metabolic acidosis.
Uremia, which develops with impaired renal function, can also raise the anion gap. When kidneys cannot remove acids adequately, retained solutes contribute to systemic acidosis. In these cases, the calculator result should be paired with renal studies, blood gas analysis, and the overall clinical picture.
Elevated anion gap results should prompt a focused diagnostic evaluation for the underlying source of acid accumulation. The key question is not only whether the gap is elevated, but why. That distinction guides urgency, treatment, and monitoring.
Normal Anion Gap Metabolic Acidosis Explained
A standard value does not exclude metabolic acidosis. It may instead suggest normal anion gap metabolic acidosis, also called hyperchloremic acidosis. In this pattern, bicarbonate is depleted, and chloride increases to preserve electrical neutrality.
Diarrhea is one of the most common causes. The gastrointestinal tract can release large amounts of bicarbonate, resulting in acidosis with a compensatory increase in chloride. This is a common example of a chloride shift that prevents the anion gap from widening.
Renal tubular acidosis is another major cause. In this disorder, the kidneys do not acidify urine correctly or do not recover bicarbonate efficiently. The result is a normal gap acidosis that may be easy to miss unless electrolytes are assessed carefully.
Normal anion gap acidosis can also occur with specific intravenous fluids or renal losses, so the surrounding context matters. If the calculator output is normal but bicarbonate is low, consider whether the picture fits hyperchloremic bicarbonate loss rather than build-up of unmeasured acids.
Knowing this separation helps separate high gap conditions from non-gap conditions, which is essential for accurate acid-base disorder classification.
Adjusted Anion Gap and Adjustment for Albumin
Albumin is a major unmeasured anion, so shifts in serum albumin can significantly affect the anion gap. When albumin is decreased, the measured gap can look normal even in the presence of clinically relevant acidosis. That is why the corrected anion gap is often more revealing than the raw value.
Hypoalbuminemia lowers the baseline anion gap. If this is not accounted for, a patient with lactic acidosis or another high-gap process may be misclassified as having a normal gap. Albumin correction helps expose hidden acid accumulation and improves clinical interpretation.
A useful bedside approach is to modify the gap for the measured albumin value before deciding whether the result is truly abnormal. Many calculators do this automatically, which is especially helpful during rapid blood gas analysis or emergency diagnostic evaluation.
The delta gap is another helpful concept in this setting. It compares the change in the anion gap with the change in bicarbonate to help identify mixed disorders. For example, a markedly elevated gap with a smaller-than-expected bicarbonate drop may suggest a concurrent metabolic process. This makes the delta gap important for deeper acid-base interpretation.
In practice, corrected values are most useful when a low albumin level could hide the true severity of the disorder. That is one reason the corrected anion gap is central to modern calculator-based assessment.
Frequent Causes of an Atypical Anion Gap
An abnormal result may indicate many different disorders, and the cause depends on whether the gap is elevated, normal, or altered by albumin status. Typical high-gap causes include toxic alcohols, salicylates, renal failure, and sepsis.
Toxic alcohols such as methanol or ethylene glycol generate acids that raise the gap and can lead to severe metabolic acidosis. These poisonings require urgent recognition because they may lead to neurologic, renal, and visual injury.
Salicylates can create a complex acid-base pattern, often including respiratory and metabolic features. They are important because they may present with a high anion gap and other changes that make the overall picture less straightforward than a simple one-lab interpretation.
Renal failure can lead to acid build-up and reduced clearance of unmeasured acids. As kidney function worsens, the anion gap may rise, and the laboratory pattern can reflect anion gap calculation worsening renal function and uremic toxin accumulation.
Sepsis is another major cause because tissue hypoperfusion can promote lactate generation and produce lactic acidosis. In that setting, the calculator output should be matched with hemodynamic status, infection markers, and the overall extent of illness.
Because different causes can coexist, the abnormal gap should be viewed as a clue, not a final answer. The next step is always to connect the number with symptoms, exposure history, and other laboratory data.
Drawbacks of Anion Gap Calculation
While the anion gap is valuable, it has important constraints. Lab variation can change the result, because different analyzers, measurement methods, and calibration standards may alter the reference range. A value deemed abnormal in one lab may be less worrisome in another.
Another limitation is that the calculation does not directly measure all physiologically important ions. Changes in ionized calcium and magnesium can alter overall electrolyte balance, but they are not part of the standard formula. This means the anion gap is only one piece of the acid-base picture.
The test also does not replace a full clinical assessment. A patient may have symptoms of acidosis despite a normal gap, or a mild gap elevation may not be clinically significant if the rest of the picture is reassuring. The overall context is important more than the number alone.
In addition, the gap can be affected by protein changes, measurement artifacts, and mixed disorders. For this reason, it is best used as a support tool alongside serum chemistry, blood gas analysis, and the rest of the diagnostic evaluation.
When to Use an Anion Gap Calculator
An anion gap calculator is most helpful when evaluating suspected acid-base disorders or unexplained low bicarbonate. It is commonly used after results from an arterial blood gas or basic metabolic panel become available, especially when the clinician wants to distinguish high-gap from normal-gap acidosis.
The calculator is especially useful when there is concern for metabolic acidosis, unexplained respiratory compensation, or a possible mixed disorder. It can help sort out whether the likely pattern is high anion gap metabolic acidosis or normal anion gap metabolic acidosis, which changes the differential diagnosis and treatment plan.
Use this calculator during the clinical evaluation of individuals with confusion, fluid loss, severe hypotension, kidney dysfunction, toxic exposure concerns, or marked electrolyte disturbances. It is also valuable when determining whether low albumin levels may be obscuring the true degree of acidosis.
For optimal accuracy, interpret the calculator output alongside the patient’s clinical history, physical findings, and serial lab results. That strategy improves detection of acid-base balance disorders and aids better decision-making in the moment.
FAQ
What is the anion gap calculator used for?
The anion gap calculator is used to support interpretation of metabolic acidosis by evaluating measured electrolytes and calculating the amount of unmeasured anions in the blood. It helps tell apart high anion gap metabolic acidosis from normal anion gap metabolic acidosis and supports clinical interpretation of abnormal serum chemistry results.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
Apply the formula: anion gap = serum sodium - (serum chloride + serum bicarbonate). In lab notation, that is often expressed using Na+, Cl-, and HCO3-. This calculation can be done by hand or with an anion gap calculator.
What does a high anion gap mean in metabolic acidosis?
A high anion gap usually means there are additional unmeasured acids in the blood, which is common of high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, uremia, toxic alcohols, and salicylates. It should always be interpreted in the context of the patient’s clinical picture.
Why do you correct the anion gap for albumin?
You modify the anion gap for albumin because hypoalbuminemia can make the gap look falsely within range. Since albumin is a major unmeasured anion, a low level can mask a true increase in acids. The corrected anion gap gives a better view of the acid-base status.
What causes a normal anion gap metabolic acidosis?
Common causes of normal anion gap metabolic acidosis include diarrhea and tubular kidney acidosis. This pattern is also called hyperchloremic acidosis because chloride increases as bicarbonate falls. It reflects bicarbonate loss or reduced acid excretion rather than a buildup of unmeasured acids.