What Is Normal Anion Gap Metabolic Acidosis?
A normal anion gap metabolic acidosis is a type of metabolic acidosis in which the anion gap is kept within the usual range even though the blood has become more acidotic. It is also called hyperchloremic acidosis or non-anion gap acidosis. The main lab feature is a decreased serum bicarbonate level, because bicarbonate is being depleted faster than the body can replace it.
This acid-base problem is usually recognized during a laboratory evaluation of symptoms such as fatigue, weakness, rapid breathing, or signs of volume depletion. Rather than a buildup of unmeasured acids, the issue is often a base loss or a problem with acid handling by the kidneys. That makes the clinical presentation and the differential diagnosis especially relevant.
The basic idea is straightforward: the body tries to preserve acid-base balance by keeping electrical charge in check while adjusting serum electrolytes. When bicarbonate falls, another negatively charged ion, usually chloride, rises to maintain balance. That is why the anion gap stays normal even though acidosis is present.
How Does the Anion Gap Stay Normal?
The anion gap shows the relationship among major serum electrolytes, especially sodium, potassium, chloride, and bicarbonate. In normal anion gap metabolic acidosis, the drop in bicarbonate is paired by a increase in chloride. This maintains electroneutrality, meaning the total charge in the bloodstream stays balanced.
That shift is why the condition is called hyperchloremic acidosis. The body is not adding large amounts of hidden acids; instead, it is dealing with bicarbonate loss or limited bicarbonate recovery. The result is a bicarbonate deficit with adaptive chloride retention or increase.
This pattern is different from high anion gap acidosis, where additional acids accumulate. Here, the problem is usually a base loss process, a kidney problem affecting renal acid handling, or both. Understanding this mechanism helps narrow the differential diagnosis rapidly.
The body also produces a compensatory response through breathing, which may lower carbon dioxide. But respiratory compensation cannot resolve the underlying electrolyte imbalance. The real answer depends on identifying whether the source is gastrointestinal, renal, medication-related, or related to normal saline exposure.
What Causes this acid-base disorder?
The most common causes involve a drop in bicarbonate from the gut or reduced ability of the kidneys to acidify the urine and take back bicarbonate. Diarrhea is a classic cause because it straightforwardly eliminates bicarbonate-rich fluid from the gastrointestinal tract. Another important group is renal tubular acidosis, where the kidneys cannot process acid effectively despite maintained or only mildly reduced overall kidney function.
Gastrointestinal bicarbonate loss is one of the most important mechanisms to understand. Stool losses can produce a distinct non-anion gap acidosis, especially when symptoms are continuing. On the kidney side, different forms of renal tubular acidosis create distinctive patterns of urine pH and urine anion gap results.
Medication and treatment effects are also common. Acetazolamide lowers bicarbonate reabsorption, while amphotericin B can injure renal tubules. Large-volume saline infusion or saline administration can thin out bicarbonate and boost chloride, creating a lab picture that looks like true bicarbonate loss.
Gastrointestinal Causes
Diarrhea is the standard gastrointestinal cause of normal anion gap metabolic acidosis. Repeated stool output leads to bicarbonate loss, which lowers serum bicarbonate and leaves the bloodstream relatively rich in chloride. The result is hyperchloremia with acidosis.
Other gastrointestinal sources include an ileostomy and a pancreatic fistula. Both can produce fluid losses that contain bicarbonate, creating a similar pattern. These are important to consider when the patient has surgery in the recent past, drainage tubes, or high-output losses.
The practical clue is usually a history of fluid loss plus signs of volume depletion. If the body is losing base faster than it can replace it, the acid-base disorder can become evident quickly. In these cases, the treatment focus is often on replacing fluids and correcting the underlying source of loss.
Kidney-Related Factors
RTA is among the main renal-related causes of normal anion gap metabolic acidosis. It suggests a defect in acid secretion in the tubules, bicarbonate reabsorption, or the two. These problems can happen even when general kidney function is not severely impaired.
Distal renal tubular acidosis happens when the time the distal nephron fails to acidify urine properly. Therefore, urine pH can stay inappropriately high despite the presence of systemic acidosis. This is a clue that urinary acidification is impaired.
Proximal renal tubular acidosis occurs when the kidney is unable to recover filtered bicarbonate efficiently. The outcome is bicarbonate wasting, especially early in the course. This form can be linked with other generalized tubular abnormalities and may appear alongside broader electrolyte imbalances.
Type 4 renal tubular acidosis is frequently associated with diminished aldosterone function, and/or resistance, which disrupts acid excretion and potassium handling. It often features hyperkalemia, which can set it apart from other forms. This is why checking potassium matters in the diagnostic workup.
Long-term kidney disease can also contribute, especially as tubular acid handling becomes less efficient. While severe kidney failure often causes a high anion gap pattern later on, earlier stages may show a normal anion gap pattern. That makes careful interpretation essential.
Medicines and Toxins
Acetazolamide is a commonly prescribed drug reason because it suppresses carbonic anhydrase and promotes bicarbonate loss in the urine. This leads to a clear bicarbonate deficit and can decrease serum bicarbonate enough to cause symptoms. It is a classic example of drug-induced non-anion gap acidosis.
Amphotericin B can harm the kidney tubules and impair acid handling, sometimes producing distal tubular dysfunction. In other words the kidneys may fail to acidify urine properly, leading to ongoing acidosis. Tracking kidney function and electrolytes is important during treatment.
Ifosfamide is another medication associated with tubular injury and bicarbonate wasting. In patients receiving chemotherapy, a new electrolyte imbalance should prompt a review of medication exposure. Drug history is often a key element of the diagnostic workup.
Saline infusion can also cause or worsen hyperchloremic acidosis. Large amounts of normal saline add chloride relative to bicarbonate, shifting the serum electrolyte pattern toward acidosis. This is especially important in patients who receive aggressive fluid resuscitation or repeated IV fluids.
How Can You Determine the Cause?
The diagnosis begins with verifying the acid-base imbalance. An arterial blood gas helps reveal the pH, carbon dioxide, and degree of metabolic compensation. Serum chemistry then verifies the low serum bicarbonate and helps assess the pattern of sodium, chloride, and potassium.
The following step is to look for the source of base loss. A high serum chloride level strongly supports hyperchloremic acidosis. If there is a history of diarrhea, an ostomy, or another gastrointestinal loss, the cause may already be apparent.
If the cause is not obvious, urine testing becomes very informative. The urine anion gap can help determine whether the kidneys are appropriately excreting ammonium, which reflects acid excretion. A negative urine anion gap often suggests an appropriate renal response, while a positive value can suggest renal tubular acidosis.
Urine pH provides another clue. In distal renal tubular acidosis, urine pH may remain too high even in the setting of systemic acidosis. Combined with the rest of the diagnostic workup, this helps distinguish kidney-related causes from gastrointestinal bicarbonate loss.
Medication review, fluid history, and kidney function testing complete the picture. In many cases, the right answer emerges only when lab data are matched with the patient’s clinical presentation.
At what time Do an Anion Gap Calculator Be Applied?
This Anion Gap Calculator is useful anytime you want to interpret acid-base data quickly and accurately. It follows the anion gap formula to available electrolytes and assists in determining whether the pattern matches a normal anion gap, a high anion gap, or a mixed disorder.
This is especially helpful when the lab picture is not clear. For example, a patient may have reduced bicarbonate but only minimal symptoms, or the chloride pattern may be altered by IV fluids. In those cases, the calculator supports better lab interpretation.
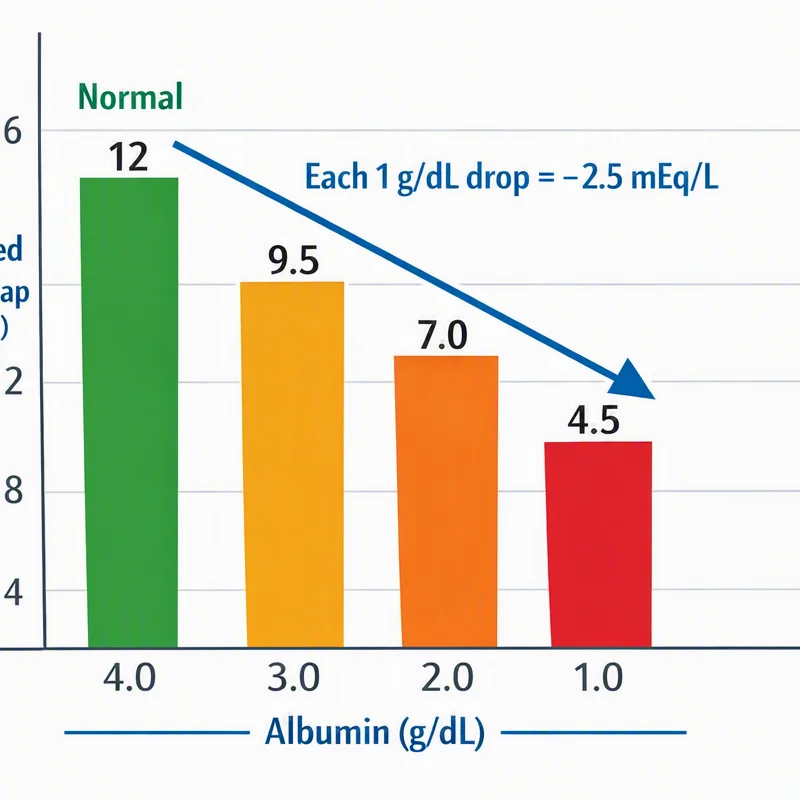
One important point is albumin correction. Decreased albumin can make the anion gap look falsely normal or low, which may conceal another acid-base problem. Correcting for albumin helps avoid failing to detect a mixed disorder.
The calculator is not a replacement for clinical reasoning, but it is an practical tool for early triage. If the numbers suggest normal anion gap metabolic acidosis, the next step is to look for gastrointestinal bicarbonate loss, renal tubular acidosis, medication effects, or saline-related changes.
How Is Treatment Managed?
Management depends on the underlying cause, but the main principle is to address the underlying cause. If serum anion gap formula the acidosis is driven by frequent diarrhea, controlling stool losses and rehydrating the patient are essential. If the cause is renal, management may involve correcting the tubular problem and supporting kidney function.
IV fluids is often needed when there is fluid loss. However, the type of fluid matters because large amounts of 0.9% saline can worsen hyperchloremia. Clinicians often choose fluids carefully to avoid increasing the acidosis.
Alkali replacement may be appropriate in selected patients, especially when acidosis is severe or ongoing losses are substantial. This does not replace causal therapy, but it can support the pH while the underlying issue is addressed.
Management of electrolytes is also important. Potassium, chloride, sodium, and magnesium may all need attention depending on the cause. Because acid-base disorders and electrolyte imbalance often occur together, treatment usually requires repeated monitoring and adjustment.
When Is Clinical Assessment Needed?
Medical evaluation is necessary when there is severe acidosis, especially if the patient has breathlessness, progressive weakness, or changed thinking. A major acid-base disorder can affect heart and brain function and should not be ignored.
Dehydration with ongoing losses, especially from significant diarrhea or losses similar to vomiting, also requires prompt attention. Rapid worsening can occur if the body cannot keep up with continued bicarbonate loss and volume loss.
Concern for kidney failure raises the stakes further, since impaired kidney function can decrease acid clearance and complicate treatment. A patient with known kidney disease or altered urine output should be assessed quickly.
Confusion, lethargy, chest symptoms, or signs of poor perfusion are warning signs. These findings suggest the body is having trouble compensating and that the acid-base disorder may be a serious concern.
Common Questions
Which cause is most common in normal anion gap metabolic acidosis?
Diarrhea is one of the most common causes because it leads to direct gastrointestinal bicarbonate loss. Such loss reduces serum bicarbonate and creates a hyperchloremic acidosis pattern with a normal anion gap.
What separates normal anion gap metabolic acidosis from high anion gap acidosis?
In normal anion gap metabolic acidosis, the problem is usually bicarbonate loss or impaired renal acid handling, so chloride rises to preserve electroneutrality. In high anion gap acidosis, unmeasured acids build up, so the anion gap formula shows an elevated gap in place of a normal one.
Does diarrhea cause normal anion gap metabolic acidosis?
Yes. Diarrhea is a well-known cause because stool contains bicarbonate, and ongoing losses cause a bicarbonate deficit. This is a common form of non-anion gap acidosis.
What urine tests help identify the cause of normal anion gap metabolic acidosis?
The most useful urine tests are the urine anion gap and urine pH. Together, they help distinguish renal tubular acidosis from gastrointestinal bicarbonate loss and show whether the kidneys are responding appropriately with acid excretion and urinary acidification.
When should an Anion Gap Calculator be used in acid-base evaluation?
An Anion Gap Calculator should be used whenever you are interpreting a low bicarbonate level or any suspected acid-base disorder. It helps with lab interpretation, supports recognition of mixed disorders, and can be paired with albumin correction for a more accurate assessment.